


Introduction
In sports, especially at high levels, injuries are frequent and can reduce key physical qualities such as strength, flexibility, sprinting capacity, and aerobic fitness [1]. Among these, ankle sprains are among the most common musculoskeletal injuries, accounting for up to 20–30% of all sports-related injuries [2]. The ankle joint plays a critical role in efficiency during functional activities and in the accurate execution of many athletic skills [2]. More specifically, dorsiflexion of the ankle is a crucial factor for the functional kinetic performance of the lower limbs, particularly in sports activities that involve dynamic movements, changes of direction, jumps, and landings [3].
Conversely, in cases of reduced ankle mobility, certain bio-mechanical changes occur that can negatively affect movement efficiency in high-performance athletes and may even lead to injuries [3]. A decrease in ankle dorsiflexion may result not only from shortening of the antagonist muscles and reduced joint play but also from displacement of the joint axis, which may help explain the heightened risk of injury [4]. Therefore, to optimise balance and jumping performance, physiotherapists and other health professionals must give particular attention to the ankle joint and its functional characteristics [5].
Several therapeutic techniques have been proposed to improve ankle dorsiflexion, with stretching being the most common [3]. Eccentric exercises can also lengthen an active muscle while it is under load [6]. In addition, the talocrural posterior glide technique is one of the fundamental mobilisations aimed at improving the ankle’s dorsiflexion range of motion (DF-ROM) [7]. This technique can be applied to enhance joint mobility [8], which is important for sports activities that require sufficient ankle motion, such as running, jumping, and rapid changes in direction [8, 9].
Previous systematic reviews provide important but incomplete context for the present question. Mason-Mackay et al. [10] synthesised evidence indicating that restricted ankle dorsiflexion is associated with altered landing biomechanics and movement strategies that may increase lower- limb loading and injury susceptibility, supporting the clinical relevance of restoring dorsiflexion. More intervention-focused syntheses have evaluated joint mobilisation effects on dorsiflexion and related functional measures: Vallandingham et al. [11] reported that joint mobilisations can produce small-to-moderate improvements in dorsiflexion in individuals with chronic ankle instability, while effects on dynamic postural control were less consistent. Most recently, Paula et al. [12] examined randomised sham-controlled trials assessing weight-bearing dorsiflexion and found a statistically significant benefit of manual therapy on dorsiflexion, but with very low certainty of evidence due to substantial heterogeneity and imprecision. Collectively, these reviews support the relevance of dorsiflexion and suggest that manual interventions may improve dorsiflexion; however, they do not specifically synthesise whether dorsiflexion gains following manual therapy translate into sport-related functional or athletic performance outcomes, leaving a clinically meaningful gap for return-to-sport decision-making.
Nonetheless, despite the expanding body of research and the availability of several systematic reviews, the evidence regarding the efficacy of manual therapy in enhancing ankle dorsiflexion and, importantly, its subsequent influence on sport-related functional and athletic performance outcomes remains inconsistent across study designs and populations. A clearer understanding of these effects is crucial for informing evidence-based rehabilitation protocols and return-to-sport decision-making.
The current review brings together existing data on manual therapy techniques applied to the ankle and examines their reported effects on dorsiflexion range of motion and sport-related functional performance. Accordingly, the objective of this systematic narrative review was to synthesise evidence on the effects of ankle joint mobilisation on dorsiflexion range of motion and to critically examine whether improvements in dorsiflexion are associated with changes in sport- related functional and athletic performance outcomes.
Subjects and methods
Literature identification and selection procedures
A structured and systematic literature search was conducted in August 2025 using PubMed/MEDLINE, the Cochrane Library, and additional grey literature repositories relevant to the topic. The electronic search covered studies published between January 2011 and December 2024. The search strategy used the following keywords: (“manual therapy” OR “joint mobilization” OR “ankle mobilization” OR “mobilization with movement” OR “Mulligan technique” OR “Maitland mobilization”) AND (“ankle” OR “ankle dorsiflexion” OR “talocrural joint” OR “ankle flexibility”) AND “athletes” AND (“range of motion” OR “sports performance” OR “athletic performance” OR “jump performance” OR “vertical jump” OR “agility” OR “landing mechanics” OR “functional performance” OR “lower limb biomechanics” OR performance). These terms were applied consistently across databases, with minor adaptations where required by database-specific indexing.
Although a comprehensive and systematic search strategy was employed, the present review was designed as a systematic narrative review, aiming to provide a qualitative synthesis of the available evidence rather than a formal systematic review or meta-analysis.
Grey literature searching was limited to targeted screening of trial registries and reference lists of relevant articles; theses, dissertations, conference proceedings, and non-peer-reviewed reports were not systematically searched.
No date or language filters were applied, other than restricting the results to peer-reviewed journal articles. Only peer-reviewed journal articles were considered for inclusion. Non-peer-reviewed materials, including books, conference papers, and reference texts, were omitted from consideration. Studies were excluded if they met any of the following conditions: (1) non-randomised or uncontrolled study designs, (2) interventions not focused on the ankle or lacking an ankle- related manual therapy component; non-English full texts; conference abstracts, and (3) studies without ankle-related functional, ROM, or performance outcomes.
Study selection
The inclusion criteria comprised: (1) participants involved in athletic or sport-related activities, irrespective of sex; (2) individuals aged between 15 and 40 years; and (3) experimental studies employing randomised or controlled designs, including full-scale and pilot randomised controlled trials. Eligible studies were required to investigate the effects of manual therapy interventions applied to the ankle joint, such as joint mobilisation techniques (e.g., Maitland mobilisations or mobilisation with movement), either as standalone interventions or as part of a multimodal rehabilitation approach. Studies focusing exclusively on stretching, exercise-only interventions, or non-manual modalities without a manual therapy component were excluded. The literature search included studies published between January 2011 and December 2024.
To be considered for inclusion, studies had to report outcomes related to ankle dorsiflexion range of motion and/or sport-related functional or athletic performance measures (e.g., balance, hopping, jumping, agility, or similar functional tests relevant to athletic activities). Observational studies, case reports, narrative reviews, and expert opinion papers were excluded.
Study selection was undertaken to support a qualitative narrative synthesis of the available evidence rather than a quantitative meta-analytic comparison.
Two independent reviewers screened all search results against the inclusion criteria, first by title and abstract, and then in full text for potentially relevant articles. Any disagreements were resolved by a third senior reviewer. The Zotero software was used for reference management, duplicate identification, and organisation of records during the screening and selection process.
Quality assessment
The quality of the selected controlled trials was appraised through the Physiotherapy Evidence Database (PEDro) scale. Based on their PEDro ratings, studies were categorised as excellent (9–10), good (6–8), moderate (4–5), or poor (< 4). A summary of these quality scores is presented in Table 1.
Table 1
Summary of methodological quality scores for the analysed studies
| Items | PEDro | |||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| 1 | 2 | 3 | 4 | 5 | 6 | 7 | 8 | 9 | 10 | 11 | total | |
| Holland et al. [13] | 1 | 1 | 1 | 1 | 1 | 1 | 1 | NR | 7 | |||
| Sohrabi et al. [14] | 1 | 1 | 1 | 1 | 1 | 1 | 1 | 6 | ||||
| Sadaak et al. [15] | 1 | 1 | 1 | 1 | 1 | 1 | 5 | |||||
| Tahir et al. [16] | 1 | 1 | 1 | 1 | 1 | 1 | 5 | |||||
| Cruz-Díaz et al. [17] | 1 | 1 | 1 | 1 | NR | 1 | 1 | 1 | 7 | |||
| Izaola-Azkona et al. [18] | 1 | 1 | 1 | 1 | 1 | 1 | 1 | 1 | 7 | |||
| Izaola-Azkona et al. [19] | 1 | 1 | 1 | 1 | NR | 1 | 5 | |||||
| Hedlund et al. [20] | 1 | 1 | 1 | 1 | NR | 1 | 1 | 1 | 1 | 8 | ||
| Kamali et al. [21] | 1 | 1 | 1 | 1 | 1 | 1 | 1 | 1 | 7 | |||
| Plaza-Manzano et al. [22] | 1 | 1 | 1 | 1 | 1 | 1 | 1 | 1 | 7 | |||
| Espí-López et al. [23] | 1 | 1 | 1 | 1 | 1 | 1 | 1 | 1 | 7 | |||
[i] 1 – eligibility criteria 2 – random allocation 3 – concealed allocation 4 – baseline comparability 5 – blind subjects 6 – blind therapists 7 – blind assessors 8 – adequate follow-up 9 – intention-to-treat analysis 10 – between-group comparisons 11 – point estimates and variability NR – not reported
Results
Study selection and general characteristics
Figure 1 presents a flow diagram detailing the study selection process. In total, 8,553 records were initially retrieved from the database searches. After duplicates had been discarded, titles and abstracts were examined to determine relevance. Subsequently, 137 studies were read in full, and 126 did not satisfy the established inclusion criteria. A total of 11 studies met the inclusion criteria and were incorporated into the narrative qualitative synthesis. Reasons for exclusion included non-randomised or uncontrolled study designs; interventions not targeting the ankle joint or lacking a manual therapy component specific to the ankle; non-English full-text availability; conference abstracts; and the absence of out- comes related to ankle function, range of motion (ROM), or athletic performance. A detailed breakdown of the number of records excluded at each stage of screening, as well as the specific reasons for full-text exclusion, is provided in the PRISMA flow diagram (Figure 1).
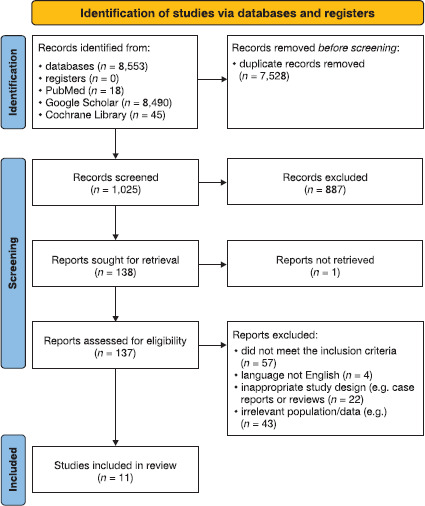
A total of 11 randomised controlled trials, involving 423 athletes, met the eligibility criteria and were included in this review. The studies varied in design, intervention protocols, and outcome measures, but all examined the effects of manual therapy or combined interventions on ankle dorsiflexion range of motion (DF-ROM), function, or athletic performance. Interventions included joint mobilisation techniques (e.g., anterior-to-posterior talar glide, mobilisation with movement, thrust manipulation), manual therapy combined with exercise programs, and adjunctive approaches such as aquatic therapy or self-mobilisation.
Across the included trials, sample sizes ranged from 16 to 56 participants per study. Participants were predominantly recreational to semi-elite athletes, with a smaller number of studies involving elite or professional athletes. The age of participants generally ranged from mid-adolescence to early adulthood. The sports represented encompassed both team- based and individual disciplines, including soccer, basketball, volleyball, handball, CrossFit, field hockey, and non-contact university sports. Most studies focused on athletes with lateral ankle sprain or chronic ankle instability, while others included participants with restricted ankle dorsiflexion or talocrural joint dysfunction. Detailed participant characteristics and study-specific attributes are presented in Table 2.
Table 2
Participant characteristics of the included studies
| Study | Sample (n) | Intervention (intervention and comparator) | Duration | Outcomes | Key findings |
|---|---|---|---|---|---|
| Holland et al. [13] | 48 athletes | grade IV anterior-to-posterior talar glide (30 s, 60 s, 120 s); uninjured limb as within-subject control | 3 sessions 5 days | WB-DF-ROM, SEBT | All groups improved; longer mobilisation time yielded greater effects. |
| Sohrabi et al. [14] | 30 athletes | corrective exercise program (mobilisation, stretching, strengthening) vs. no treatment | 8 weeks | ROM, proprioception, Y-Balance Test | Significant improvements in ROM, balance, proprioception, and muscle activation in experimental group. |
| Sadaak et al. [15] | 30 athletes | aquatic therapy vs. conventional PT | 4 weeks | VAS, hop tests, agility, SEBT | Aquatic therapy group showed superior pain reduction, hop performance, balance, and faster return to sport. |
| Tahir et al. [16] | 16 athletes | thrust manipulations vs. non-thrust mobilisation | 8 weeks | GRC, FAAM | Thrust manipulation significantly superior for function (p < 0.001). |
| Cruz-Díaz et al. [17] | 49 athletes | CrossFit + self-mobilisation vs. CrossFit only | 12 weeks | WBLT, SEBT, CAIT | Both groups improved; self-mobilisation group superior for DF-ROM and SEBT PL/PM. |
| Izaola-Azkona et al. [18] | 45 athletes | MOB vs. MWM vs. MWM + tape | 6 sessions 2 weeks | FAAM, ROM, strength | MWM and MWM+tape yielded superior long-term function; MOB superior at 2 weeks. |
| Sankaravel et al. [19] | 18 athletes | MWM vs. placebo mobilisation | 6 weeks | DF-ROM, dynamic balance | Greater improvements in ROM and balance in experimental group. |
| Hedlund et al. [20] | 19 athletes | HVLA talocrural manipulation vs. sham | 3 sessions 3 weeks | vertical jump height | Significant improvement in jump height in experimental group; not in sham group. |
| Kamali et al. [21] | 40 athletes | talocrural quick thrust vs. sham | 3 sessions | hop tests, Y-Balance Test | Experimental group showed significant functional gains vs. control. |
| Plaza- Manzano et al. [22] | 56 athletes | proprioceptive + strengthening + manual therapy vs. exercise alone | 4 weeks | VAS, CAIT, strength, ROM | Both improved, but experimental group showed greater reductions in pain and increases in ROM and strength. |
| Espí-López et al. [23] | 42 athletes | manual therapy vs. PNF | 3 sessions 3 weeks | SEBT, ROM, flexibility | Both improved; manual therapy effects lasted longer, with greater ankle DF-ROM gains. |
[i] CAIT – Cumberland Ankle Instability Tool, DF-ROM – dorsiflexion range of motion, FAAM – Foot and Ankle Ability Measure, GRC – Global Rating of Change, HVLA – high-velocity, low-amplitude, MOB – mobilisation, MWM – mobilisation with movement, PNF – proprioceptive neuromuscular facilitation, PT – physical therapy, ROM – range of motion, SEBT – Star Excursion Balance Test, VAS – Visual Analogue Scale, WB-DF-ROM – weight-bearing dorsiflexion range of motion, WBLT – Weight-Bearing Lunge Test
Effects of manual therapy on ankle dorsiflexion range of motion, balance, and athletic performance
Holland et al. [13] examined the acute effects of different joint mobilisation treatment durations on ankle DF-ROM and dynamic postural control in collegiate female athletes with chronic ankle instability (CAI). In this randomised controlled laboratory study, 48 athletes (mean ± SD age, 22.80 ± 4.80 years) were allocated to one of three groups based solely on mobilisation duration per session: 30 s (n = 16), 60 s (n = 16), or 120 s (n = 16). All participants received the same intervention – a Maitland Grade IV anterior-to-posterior talar glide performed with 1-second rhythmic oscillations – applied across three treatment sessions delivered over five days, with sessions spaced 48 hours apart. The only experimental difference between the groups was the duration of the mobilisation applied during each session. Primary outcome measures included DF-ROM, WB-DF-ROM, posterior talar glide (PG), and dynamic balance assessed using the SEBT. Significant improvements were observed across all outcomes following each treatment session, with longer mobilisation durations producing progressively greater gains. Between- group differences were evident after sessions 1, 2, and 3, with the 120-s protocol demonstrating the largest effect sizes for WB-DF-ROM, PG, and anterior SEBT reach. The authors concluded that ankle joint mobilisation induces meaningful acute improvements in ankle mobility and postural control in athletes with CAI, and that treatment duration is a key parameter influencing the magnitude of these effects.
Sohrabi et al. [14] investigated the effects of a comprehensive corrective exercise program on ankle function in female athletes with limited weight-bearing ankle dorsiflexion. Thirty athletes aged 15–25 years with dorsiflexion < 34° were randomised into an intervention group (n = 15) or a control group (n = 15). The intervention group completed an eight-week comprehensive corrective exercise program consisting of warm-up, soft-tissue mobilisation, joint mobilisation, stretching, and strengthening exercises, while the control group received no intervention. Pre- and post-intervention assessments included ROM, proprioception, dynamic balance, and muscle activation. Results showed that the intervention group had significant improvements in ankle DF-ROM, balance, and proprioception. Muscle activity analysis revealed significant increases in tibialis anterior and soleus activation during both phases of the squat, with decreased medial gastrocnemius activity in the descending phase. The authors concluded that a comprehensive corrective exercise program effectively enhances dorsiflexion ROM, proprioception, and balance, while modulating ankle muscle activity in individuals with restricted dorsiflexion. These adaptations may contribute to reducing the risk of ankle sprains.
Sadaak et al. [15] primarily investigated the efficacy of aquatic therapy compared with a conventional physical therapy program in elite athletes with acute grade III ankle sprains. This randomised controlled trial included 30 professional athletes (aged 18–30 years) who sustained a grade III sprain within the previous 1–7 days, most of whom participated in overhead sports such as volleyball and basketball. Athletes were randomly allocated to an aquatic therapy group (n = 15) or a control group (n = 15) receiving conventional physical therapy. Both interventions were delivered over a four-week period. The conventional physical therapy program, used in the control group, comprised immobilisation, low-level laser therapy, lymphatic drainage, therapeutic and stretching exercises, neuromuscular training, postural re-education, balance training, and manual therapy, whereas the aquatic therapy program included warm-up, mobility and strengthening exercises, proprioceptive training, and functional drills. Thus, although manual therapy was not the experimental intervention, it formed part of the standard rehabilitation approach in the comparison group. Pain and functional outcomes were assessed immediately following injury and at weeks 4 and 6. Dynamic balance, athletic performance, and muscular power were evaluated at weeks 4 and 6, while time to return to sport was documented at week 4. Outcome measures included VAS, SEBT, hop performance tests, agility tests, muscle power, and return-to-sport time. The results demonstrated significant interaction effects favouring aquatic therapy for pain reduction, hop performance, agility, and dynamic balance, as well as a significantly earlier return to sport compared with conventional physical therapy. Within the context of the present review, this study provides contextual information regarding functional and athletic outcomes following rehabilitation programs in which manual therapy constitutes part of standard care, although the specific effects of manual therapy cannot be isolated.
Tahir et al. [16] compared the effects of thrust manipulation and non-thrust mobilisation on functional deficits in athletes with CAI. This randomised controlled trial included 16 athletes from the Pakistan Sports Board Complex and the Model Town Football Club, who were randomised into two groups and treated over an eight-week period (24 sessions, three sessions per week). Group A received high-velocity thrust manipulations of the proximal and distal tibiofibular joints and the talocrural joint, which was also treated with a distraction thrust. Group B received non-thrust interventions, consisting of low-velocity anteroposterior mobilisation of the talo-cuneiform joint and non-thrust lateral glide and eversion applied to the hindfoot. Outcome measures were obtained at baseline and following the 8-week intervention period, including the Global Rating of Change (GRC) and the Foot and Ankle Ability Measure (FAAM). Results indicated significant post-intervention differences between groups on both outcome measures, favouring thrust manipulation. The authors concluded that although both thrust and non-thrust mobilisation techniques improved function, thrust manipulation demonstrated superior clinical and statistical efficacy in enhancing functional capacity in athletes with chronic ankle sprain.
Cruz-Díaz et al. [17] examined the effect of adding ankle joint self-mobilisation to CrossFit training in recreational athletes with CAI. Their randomised controlled trial included 70 athletes who were randomly allocated into three groups: a CrossFit plus self-mobilisation group (n = 25), a Cross-Fit-only group (n = 24), and a control group (n = 21). The trial was conducted over a 12-week period, during which participants completed a total of 24 intervention sessions, scheduled at a frequency of two sessions per week. The CrossFit-only group followed a standard protocol consisting of a warm-up (cardiovascular activity, dynamic stretching, and progressive-load exercises), principal training/workout of the day (WOD) (strength, endurance, agility, and functional mobility), and a cool-down (light cardiovascular activity and foam rolling). The CrossFit plus self-mobilisation group followed the same CrossFit protocol with the addition of self-mobilisation techniques, including ankle joint mobilisation with resistance bands, kettlebell dorsiflexion, and band pull exercises. The control group did not receive any intervention. Primary outcome measures included ankle DF-ROM, perceived ankle instability, and dynamic postural control, evaluated using the Weight-Bearing Lunge Test (WBLT), the Cumberland Ankle Instability Tool (CAIT), and the SEBT, respectively. After 12 weeks, both intervention groups exhibited significantly greater improvements in all outcomes compared to the control group. The combined CrossFit plus self- mobilisation program was more effective than CrossFit alone for increasing DF-ROM and improving posterolateral and posteromedial SEBT reach distances, although no significant differences were found for the anterior reach or CAIT scores. The authors concluded that both CrossFit training and self- mobilisation are effective interventions for enhancing DFROM, dynamic postural control, and perceived ankle instability in individuals with CAI, with the combination of both approaches yielding superior outcomes.
Izaola-Azkona et al. [18] evaluated the immediate and sustained efficacy of talar and distal fibular mobilisation in amateur soccer players with acute lateral ankle sprains. This double-blind randomised controlled trial included 45 athletes (mean age, 24.1 ± 5.3 years) who presented with an acute sprain (< 72 hours). Participants were randomly allocated to three groups: group 1 (MOB; n = 15), which received anteroposterior mobilisation of the talocrural joint; group 2 (MWM; n = 16), which received distal fibular mobilisation with movement; and group 3 (MWM tape; n = 14), which received distal fibular mobilisation with movement combined with posterior gliding fibular taping. The intervention lasted two weeks, with six sessions delivered three times per week. Primary outcomes were self-reported function, assessed with the FAAM and the Patient Global Impression of Improvement (PGI-I) scale, measured over a 52-week follow-up. Secondary outcomes included ankle pain (VAS), pressure pain threshold (PPT), ROM, strength, and volume. Although some participants were lost to follow-up, all were included in the final analysis. The results showed that both MWM and MWM tape were equally effective and led to superior FAAM scores at 12 and 52 weeks compared with MOB, which demonstrated better outcomes only at two weeks. No significant differences between groups were observed for the PGI-I or any of the secondary outcome measures. The authors concluded that in acute lateral ankle sprains, distal fibular mobilisation with movement is more effective for improving long-term daily and sport function, while talar anteroposterior mobilisation may provide short-term benefits. Fibular taping did not provide additional benefits.
Sankaravel et al. [19] investigated the effects of a mobilisation-with-movement and exercise program (MobEx) on university athletes engaged in non-contact sports who had sustained lateral ankle sprains. Twenty-seven male and female athletes aged 19–26 years were allocated at random into an experimental group (n = 9), a placebo group (n = 9), or a control group (n = 9). The experimental group received the MobEx intervention, which combined MWM and proprioceptive balance exercises. Athletes performed MWM in a semi-flexed standing position, with a mobilising force applied to the talocrural joint while executing walking-like movements. This was followed by a progressive proprioceptive balance training program, beginning with simple tasks and advancing in difficulty based on individual tolerance. Each session also included warm-up and cool-down exercises. The placebo group received a sham mobilisation without mobilising force, and the control group received no intervention. The intervention lasted six weeks, with a follow-up assessment conducted one month later. Outcome measures included DF-ROM, assessed with the WBLT, and dynamic balance, evaluated with the Modified Bass Test. The results demonstrated significant improvements in both DF-ROM and dynamic balance in the experimental group, as well as improvements in dynamic balance in the placebo group. Gains in the experimental group were maintained at both six weeks and the one-month follow-up, suggesting that the MobEx program is effective for enhancing and sustaining ankle DF-ROM and dynamic balance in athletes with lateral ankle sprains.
Hedlund et al. [20] conducted a single-blind, randomised clinical pilot trial to investigate the effects of chiropractic high-velocity, low-amplitude (HVLA) manipulation on vertical jump height in young female athletes with talocrural joint dys-function. Their study included 22 female handball players older than 16 years of age with talocrural dysfunction, who were randomised into two groups: a corrective HVLA manipulation group (n = 11) and a sham HVLA manipulation group (n = 11). Nineteen participants completed the study, resulting in 11 athletes in the intervention group and 8 in the sham group for the final analysis. The intervention protocol consisted of three weekly sessions delivered over three weeks. The corrective HVLA group received a long-axis HVLA manipulation of the talocrural joint, whereas the sham group received HVLA manipulation applied to the distal portion of the tibia, which did not affect the talocrural joint. The primary outcome was the change in single-leg vertical countermovement jump height (in cm) from baseline to follow-up. Vertical jumps were recorded using an optoelectronic infrared system. Results indicated that the HVLA manipulation group showed a statistically significant improvement in jump height over the three weeks, whereas the sham group demonstrated only a small, non-significant increase. Although the between- group difference slightly favoured HVLA manipulation, it did not reach statistical significance. No adverse events were documented, and the feasibility of both the blinding and sham procedures was successfully confirmed. The authors concluded that chiropractic HVLA manipulation may enhance vertical jump performance in young female athletes with talocrural dysfunction. However, they emphasised that the observed between-group difference requires confirmation in larger, adequately powered randomised clinical trials.
Kamali et al. [21] conducted a double-blind randomised clinical trial to investigate the immediate effects of talocrural joint manipulation (TCJM) on functional performance in athletes with CAI. Forty semi-elite athletes (soccer, volleyball, basketball, and martial arts) aged 15–40 years with CAI were randomly assigned to a TCJM group (n = 20), or a sham manipulation group (n = 20). The TCJM group received a quick posterior thrust applied to the talus, while the sham group underwent the same positioning but without the thrust, simulating the procedure for one minute. Both groups received three intervention sessions, one per day. The primary outcome was functional performance, evaluated with the Single-Hop Test, Speed Test, and Y-Balance Test, assessed before and after the interventions. Results showed significant improvements across all functional tests in the TCJM group, whereas no meaningful changes were observed in the sham group. Between-group analyses further confirmed significant post-intervention differences favouring TCJM. The authors concluded that TCJM may improve functional performance in athletes with CAI and could represent a valuable adjunctive treatment regimen.
Plaza-Manzano et al. [22] conducted a randomised controlled trial to compare the effects of proprioceptive and strengthening exercises alone versus the same exercises combined with manual therapy, including joint and nerve mobilisations, in the management of recurrent ankle sprains. Fifty-six patients aged 20–38 years with recurrent ankle sprains and habitual athletic participation were randomly assigned to an experimental group (n = 28) or a control group (n = 28). The experimental group performed proprioceptive and strengthening exercises supplemented with manual therapy. The manual therapy protocol included mobilisations of the talocrural and distal tibiofibular joints, as well as neuro-dynamic mobilisation of the superficial peroneal nerve. Neurodynamic techniques were applied with the ankle in plan-tarflexion-inversion combined with a straight-leg raise to selectively stress the peroneal division of the sciatic nerve. All mobilisations were performed at Maitland grade III, involving large-amplitude passive movements within the participants’ tolerance. The control group received only proprioceptive and strengthening exercises. Both groups followed their respective protocols for four weeks. Primary outcomes included pain intensity (VAS), self-reported functional ankle instability (CAIT), pressure pain threshold (PPT), ankle muscle strength, and active ROM, all assessed before the intervention, immediately after, and one month later. Results demonstrated improvements over time in both groups. However, the experimental group showed significantly greater benefits, including reduced pain, lower CAIT scores, and higher PPT, muscle strength, and ROM both immediately post-intervention and at the one-month follow-up. The authors concluded that integrating manual therapy targeting joint and neural structures with proprioceptive and strengthening exercises results in superior clinical outcomes compared to exercise alone.
Espí-López et al. [23] conducted a randomised controlled trial to evaluate the comparative effectiveness of a manual therapy protocol and a proprioceptive neuromuscular facilitation (PNF) stretching protocol for enhancing dynamic balance, active ROM, and lumbar flexibility among field hockey players. Forty-two amateur players aged 16–30 years were assigned randomly to a manual therapy group (n = 22) or a PNF group (n = 20, control). The interventions were delivered once per week for three weeks, for a total of three sessions. The manual therapy protocol consisted of sequential bilateral application of the following: (a) lumbopelvic thrust manipulation applied on the right side in the lateral decubitus position (maximum two thrusts per side); (b) anteroposterior non-thrust manipulation of the hip (25 repetitions, supine); (c) lateral-to-medial non-thrust manipulation of the knee (25 repetitions, supine); (d) proximal tibiofibular joint anteroposterior non-thrust manipulation (25 repetitions, supine); (e) rear-foot distraction thrust manipulation (maximum two thrusts, supine); (f) stretching of the hip external rotator muscles; and (g) fascial manipulation in the patellofemoral region. The PNF group performed bilateral contract–relax stretching of the hamstrings, psoas, adductors, piriformis, gluteus medius, quadriceps, and rectus femoris muscles. Primary outcomes included dynamic balance (SEBT), active ROM (manual goniometer), and lumbar flexibility (Fingertip-to-Floor Test, FFT). Assessments were performed at one and four weeks following the intervention. The results showed that both groups demonstrated significant improvements in lateral and medial dynamic balance at one week. However, only the manual therapy group maintained these improvements at four weeks. Additionally, the manual therapy group showed significant increases in ankle dorsiflexion at four weeks and in lumbar flexibility at one week. The authors concluded that while both manual therapy and PNF protocols enhanced short-term dynamic balance, manual therapy provided longer- lasting improvements and additional benefits in ankle mobility and lumbar flexibility.
Overall, the methodological quality of the included studies ranged from moderate to good, as shown by the PEDro scores presented in Table 1. Most trials adequately reported eligibility criteria, random allocation, baseline comparability, and between-group comparisons. However, blinding of participants and therapists was rarely achieved, which is a common limitation in manual therapy trials. In addition, assessor blinding and intention-to-treat analysis were inconsistently reported across studies. These methodological considerations should be taken into account when interpreting the magnitude and consistency of the reported effects.
Synthesis of outcomes across studies
Across the included trials, manual therapy interventions targeting the ankle joint were consistently associated with improvements in dorsiflexion range of motion, irrespective of the specific mobilisation technique applied [13, 14, 17, 19, 22]. Increases in DF-ROM were reported following non-thrust mobilisation approaches, including mobilisation-with-movement and joint mobilisation protocols [19, 22], and were observed across acute, subacute, and chronic ankle conditions, including lateral ankle sprain and chronic ankle instability [13, 18, 19]. Improvements in dynamic balance outcomes were frequently documented across the included trials, most commonly when assessed using the Star Excursion Balance Test or the Y-Balance Test [13, 17, 21], as well as with other validated balance assessments [19, 23]. However, the magnitude and persistence of these effects varied across studies and follow-up periods [17–19].
In contrast, the findings related to athletic performance outcomes were more heterogeneous. While several studies reported short-term improvements in functional performance measures such as hopping ability, agility, vertical jump height, or return-to-sport time following interventions that included ankle mobilisation or manipulation [15, 20, 21], other trials demonstrated modest or non-significant between-group differences, particularly in underpowered or pilot designs or when performance outcomes were secondary measures [17, 18, 20]. Notably, studies employing combined interventions – integrating manual therapy with strengthening, balance, or neuromuscular training – tended to report more consistent functional outcomes and selected performance-related benefits compared with manual therapy or exercise delivered in isolation [14, 17, 19, 22]. Overall, although ankle mobilisation was associated with favourable changes in selected functional and performance-related measures, the translation of dorsiflexion gains into direct athletic performance outcomes appeared variable and context-dependent across studies [15, 20, 21].
Overall, the results indicate a robust and relatively consistent effect of manual therapy on ankle dorsiflexion and balance-related outcomes, whereas its translation into direct athletic performance gains appears more variable and context-dependent, influenced by the intervention dosage, comparator conditions, and outcome selection.
Discussion
This systematic narrative synthesis of RCTs evaluated joint mobilisation, manipulation, and complementary exercise strategies for athletes with lateral ankle sprain or CAI. Across the eleven trials reviewed, manual therapy was generally associated with improvements in DF-ROM and dynamic balance, and appeared to enhance functional outcomes when combined with targeted exercise interventions [13, 17, 22].
A dose–response trend was observed for anteroposterior talocrural mobilisation: in female athletes with CAI, three sessions lasting 30, 60, or 120 seconds each of Maitland grade IV mobilisation produced progressively greater improvements. The WB-DF-ROM improved by approximately 15.8%, 26.7%, and 43.6%, respectively, with parallel increases in posterior talar glide and SEBT reach [13]. HVLA manipulation may also induce short-term performance changes. In young handball players with talocrural dysfunction, vertical jump height increased by 1.07 ± 1.23 cm after three weekly treatments compared with an increase of 0.59 ± 2.03 cm in the sham group. The comparative difference across groups was 0.47 cm (95% CI −1.31 to 2.26), suggesting potential benefits, albeit with substantial imprecision, which is consistent with the pilot nature of the study [20].
Technique choice appears to be time-dependent in acute injury. In amateur soccer players treated within 72 hours of injury, distal fibular MWM (with or without posterior-glide taping) yielded superior FAAM scores at 12 and 52 weeks compared with anteroposterior talar mobilisation, whereas the latter produced better sport-related function at two weeks [18].
In chronic presentations, adding joint and nerve manual therapy to proprioceptive-strengthening exercise was superior to exercise alone for pain, mechanosensitivity, strength, and ROM, both immediately and at one-month follow-up [22]. A double-blind trial also reported immediate but modest improvements in single-leg hop, speed, and the Y-Balance Test following talocrural manipulation compared with sham [21]. An athlete-centred corrective exercise bundle (soft-tissue work, joint mobilisation, stretching, strengthening) delivered moderate effects on DF-ROM (ES = 0.714), balance (ES = 0.423), and proprioception (ES = 0.253), along with favourable changes in electromyography activity in women with limited WB-DF [14]. For team-sport athletes, manual therapy was more effective than proprioceptive neuromuscular facilitation for sustained improvements in dynamic balance and dorsiflexion at four weeks [23]. Self-mobilisation combined with neuromuscular training (CrossFit) further improved DF-ROM and posteromedial and posterolateral SEBT reach compared with training alone [17].
A pragmatic adjunct in early rehabilitation, aquatic therapy reduced time to return-to-sport (4.7 vs. 7.7 weeks) and decreased pain and oedema when combined with land-based therapy [15]. A head-to-head comparison favoured thrust over non-thrust techniques for pain reduction (NPRS from 9.37 ± 0.74 to 2.75 ± 1.03 vs. 7.37 ± 1.40 to 4.37 ± 1.30; p = 0.01) in athletes with chronic ankle sprain [16], while a multi- session MWM program (MobEx) improved dorsiflexion and dynamic balance, with effects retained at one month [19].
Notably, although improvements in DF-ROM were consistently observed across studies, their translation into measurable athletic performance outcomes was not uniform and appeared to be influenced by sport-specific demands, outcome selection, and the timing and context of the assessment. Therefore, improvements in ankle dorsiflexion should be interpreted as a facilitating factor rather than a direct determinant of athletic performance.
From an anatomical and kinesiological perspective, improvements in ankle dorsiflexion may influence athletic performance by modifying talocrural joint mechanics and lower-limb movement strategies. Restricted dorsiflexion has been shown to limit the ability to translate the tibia over the foot and to lower the centre of mass during squat- and landing-type movements, resulting in altered sagittal- and frontal-plane kinematics, including increased knee valgus and modified joint coordination patterns [10, 24]. Conversely, greater dorsiflexion capacity may facilitate larger joint excursions and more favourable sagittal- and frontal-plane alignment of the ankle and knee during landing tasks, which may contribute to more effective movement strategies and potentially improved shock attenuation, thereby limiting the need for compensatory movement patterns at proximal joints [24].
In dynamic landing-related tasks, dorsiflexion appears to influence overall movement patterns and force attenuation strategies rather than isolated kinematic or kinetic variables, which may partly explain the inconsistent relationships observed across individual outcome measures in the literature [10]. Importantly, the translation of dorsiflexion improvements into measurable athletic performance gains appears to be modulated by sport-specific demands, fatigue status, and contextual factors related to neuromuscular readiness rather than dorsiflexion changes in isolation. Observational evidence from team-sport athletes suggests that fluctuations in ankle dorsiflexion range of motion are closely linked to competitive load, seasonal fatigue, and injury risk profiles, which may indirectly influence performance expression rather than directly enhancing performance outputs [25, 26].
Mechanistically, higher-grade mobilisations are thought to induce plastic deformation of periarticular tissues, with increased posterior talar glide facilitating dorsiflexion-dependent tasks. Concurrently, neurophysiological mechanisms, including hypoalgesia and short-term motor control modulation, may underlie immediate functional improvements [13, 21, 22].
The evidence reviewed suggests several important clinical considerations. First, the treatment dose appears to matter: protocols employing two-minute Maitland grade IV sets may provide the most pronounced and rapid gains in WBDF-ROM among athletes with CAI. Second, the choice of technique should be aligned with the stage of injury. In the acute phase, talar anteroposterior mobilisation may support early recovery of sport-related function, whereas in the sub-acute to chronic stages, distal fibular MWM appears more effective for achieving superior FAAM scores over the medium to long term. Finally, manual therapy alone is unlikely to be sufficient; it should be integrated with strengthening, balance, and mobility training, including corrective exercise strategies. Moreover, adjunctive approaches such as aquatic therapy may further accelerate recovery by facilitating early loading and promoting a faster return-to-play trajectory.
Despite these promising findings, several limitations of the available evidence warrant caution in interpretation. Many of the included trials were small in sample size or pilot in design, often with short follow-up periods that restrict conclusions about long-term effectiveness. The heterogeneity of sport cohorts and outcome measures further complicates the ability to generalise findings across athletic populations. Methodological concerns were also evident, as allocation concealment and therapist blinding were frequently unclear. In addition, two of the included studies were published in journals with variable indexing status and impact (e.g., EJMCM; IJHS), which may affect confidence in their results. Moreover, the reliance on a qualitative narrative synthesis, in the absence of quantitative meta-analytic pooling, limits the precision of effect estimation. Taken together, these limitations underscore the need for cautious interpretation and highlight the importance of conducting larger, methodologically rigorous, sport-specific randomised controlled trials to strengthen the evidence base.
Conclusions
The available evidence suggests that ankle mobilisation and manipulation are associated with improvements in DFROM and dynamic balance, with longer-duration grade IV talar mobilisation tending to produce the greatest immediate effects. In acute sprain, distal fibular MWM may be most effective for optimising longer-term function, whereas talar anteroposterior mobilisation appears to support early sport- related recovery. When integrated with well-structured exercise programs – and, where appropriate, aquatic loading – manual therapy may contribute to accelerated recovery and context-specific performance-relevant outcomes. Future research should refine optimal dosing parameters, clarify underlying mechanisms, and evaluate integrated rehabilitation protocols against return-to-play timelines in well-designed, sport-specific randomised controlled trials.

