

Introduction
Scoliosis and other spinal deformities represent a significant public health concern, particularly among paediatric and adolescent populations. The global prevalence of scoliosis, i.e., a three-dimensional spinal deformity, ranges from 1% to 4% during the growth period [1–5]. The most common form, adolescent idiopathic scoliosis (AIS), is a complex condition with a multifactorial aetiology involving genetic predispositions and biomechanical factors [1]. Early detection and timely intervention are crucial for preventing spinal curve progression, which can lead to severe health complications, such as chronic pain, reduced lung function, and significant psychosocial distress [4, 6–8].
School screening programmes are a widely recognized public health tool for the early identification of spinal deformities. These programmes have been instrumental in detecting scoliosis at an early stage when conservative, non-invasive treatments, such as bracing and physical therapy, are most effective [9–11]. Although their universal implementation has been a subject of debate due to cost-effectiveness and false- positive rates, many countries continue to advocate their use as a means to reduce the need for more invasive surgical interventions later in life [12, 13]. Recent studies have reaffirmed the value of these programmes, with large-scale screenings in different regions of the world highlighting their effectiveness in early diagnosis [13–16].
In Albania, information on epidemiology of spinal deformities remains extremely limited. The most recent nationwide data come from the Health Behaviour in School-Age Children (HBSC) survey conducted by the Albanian Institute of Public Health, which provided some insight into the prevalence of musculoskeletal issues and reported that 27.3% of school-children aged 11, 13, and 15 years experienced back pain [17]. Although AIS is typically considered a painless condition, the presence of back pain in adolescents with scoliosis should be regarded as a clinical red flag that warrants careful evaluation to exclude non-idiopathic or other underlying pathological causes. At the same time, epidemiological studies consistently indicate that adolescents diagnosed with scoliosis report back pain more frequently than their peers without scoliosis, with greater spinal deformities being associated with higher pain intensity [18–21]. However, these data do not provide information on the prevalence of scoliosis or other postural deformities in Albania. Consequently, the true epidemio-logical burden of these conditions among Albanian children and adolescents remains unknown, highlighting the urgent need for systematic population-based research.
This study aimed to address this knowledge gap by investigating the prevalence of postural deformities among secondary school students aged 10 to 15 years attending public schools in Tirana, Albania. The findings from this research will provide a critical epidemiological baseline for public health authorities and medical professionals, supporting the development of targeted, evidence-based strategies for screening, prevention, and treatment of spinal and postural issues in the Albanian paediatric population. By establishing the first comprehensive prevalence rate from Albania, this study will also contribute to the broader body of international literature on adolescent spinal health and underscore the importance of early intervention in preserving the long-term well-being of future generations.
Subjects and methods
This research employed a cross-sectional study design, which is ideal for determining the prevalence of a condition in a defined population at a specific point in time. The study was conducted between January and May 2024 and involved a sample of 2,020 students aged 10 to 15 years (grades 5–9) from nine public secondary schools in Tirana, Albania. This age group is particularly relevant as it encompasses the period of rapid adolescent growth, where the risk of scoliosis progression is the highest. All participants were required to be present in physical education classes and to provide written parental consent and student assent, adhering to the ethical standards for research involving minors.
Ensuring the ethical integrity of the study was a top priority. Ethical approval was obtained from the Ethics Committee of the Sports University of Tirana, and official permission was secured from the Ministry of Education and Sport. These approvals are mandatory for any research conducted on schoolchildren in Albania, confirming adherence to national and institutional ethical guidelines. All data were collected anonymously to protect the privacy and confidentiality of the participants. This ethical approach is consistent with international standards for research involving human subjects, particularly minors.
The screening process involved a combination of clinical examinations and objective measurements for the identification of spinal deformities.
Adams Forward Bend Test (AFBT)
The initial screening for scoliosis was performed using the AFBT, a well-established and widely used method for detecting trunk asymmetry [9, 22]. The test required each student to bend forward at the waist, while the examiner observed for any unevenness in the rib cage or back.
Scoliometer measurement and examiner
In participants with a positive AFBT, axial trunk rotation (ATR) was quantified using a handheld scoliometer (Baseline® Economy Scoliometer, Model 12-1099). To identify the true peak of the deformity (the gibbosity), a dynamic scanning (sliding) technique was employed rather than a single static measurement [23]. The measurement was performed by sliding the scoliometer slowly and continuously along the entire length of the spine, from the upper thoracic region to the lumbar base, while ensuring the device remained strictly perpendicular to the spinal axis at all times (Figure 1).
Figure 1
Illustration of the Adams Forward Bend Test and scoliometer application, (a) The scoliometer is aligned over the spinous processes to measure trunk rotation; the examiner stabilizes the device laterally using both hands, maintaining light contact to ensure horizontal alignment without applying downward pressure, (b) Patient positioned in the Adams Forward Bend Test with correct scoliometer placement (the procedure is demonstrated by an adult model for ethical compliance).
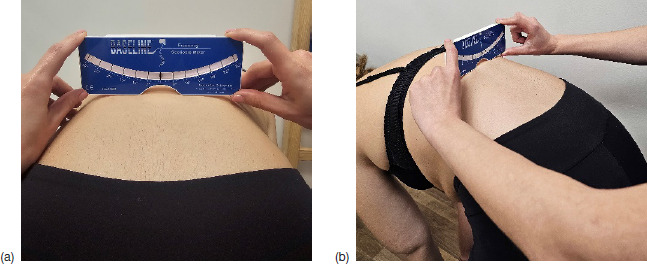
Throughout the process, the scoliometer base maintained direct and continuous contact with the participant’s skin. The examiners placed their thumbs laterally on the device as stabilizing guides to ensure a steady, fluid motion and to prevent lateral drifting. This manual stabilization ensured the scoliometer’s central notch remained aligned with the spinal midline while preventing the ‘stuttering’ effect often associated with plastic-to-skin contact during a continuous slide. This standardized method allowed for the precise identification and recording of the maximum ATR at the thoracic apex, the thoracolumbar junction, and the lumbar apex. The reliability of this technique was confirmed through a validation sub-study on 10 subjects, which demonstrated excellent agreement with the standard static skin-contact method (see Appendix for detailed validation data).
A scoliometer reading of 7° was used as the threshold for a participant to be considered screen-positive for significant trunk asymmetry, indicating a requirement for referral for further radiographic evaluation. This threshold is a widely accepted cutoff point for referral and has been reported to provide high sensitivity (84.3%) and specificity (93.44%) for identifying individuals with a Cobb angle of 10°or greater on an X-ray, which is the official radiographic criterion of scoliosis [24–26].
All screenings and measurements were performed by a specialized team of seven licensed physiotherapists. The team consisted of two researchers holding a PhD in Physiotherapy and five PhD candidates in Physiotherapy, all of whom had more than five years of clinical experience in orthopaedic manual therapy and spinal deformity screening. Prior to the study, the examiners participated in a standardized training session to ensure high inter-rater reliability, acknowledging that the accuracy of scoliometer readings is highly dependent on operator expertise.
Sagittal plane assessment (D’Osualdo arcometer)
Thoracic kyphosis and lumbar lordosis were evaluated using a D’Osualdo arcometer (Figure 2), a manual non-invasive instrument designed to measure spinal curvatures in the sagittal plane [27–29].
Figure 2
Illustration of the D’Osualdo arcometer application for sagittal plane measurement (demonstrated by an adult model for ethical compliance)

– Procedure and landmarks: Measurements were performed with the participant standing in a relaxed, spontaneous posture with arms at their sides. The examiners identified and marked the following spinous process landmarks via palpation: T1 and T12 for the thoracic curve, and L1 and L5 for the lumbar curve.
– Measurement technique: The arcometer’s two outer arms were positioned on the upper and lower limit vertebrae (e.g., T1 and T12), defining the chord. The central mobile arm was then adjusted to touch the apex of the curvature, providing the rise measurement.
– Calculation and interpretation: These linear values (chord and rise) were used to calculate the surface Cobb angle and the radius of the curvature using standardized trigonometric formulas or an accompanying two-entry conversion table.
– Diagnostic thresholds: For this study, thoracic hyper-kyphosis was defined as an angle of 40°.
Although radiographic examination remains the gold standard for the diagnosis of scoliosis, the screening methods used in this study are appropriate for large-scale school-based epidemiological investigations. They enable efficient and safe identification of students who may require further, more definitive medical evaluation. The comprehensive approach to the assessment strengthens the validity of the study’s findings and provides a robust methodology for determining the prevalence of these conditions.
Data collection for confounding variables (assessment of physical activity and sports participation)
To evaluate potential environmental factors associated with spinal asymmetry, data were collected regarding students’ involvement in extracurricular sports. This was achieved through a standardized, self-developed questionnaire completed by the participants during the screening process and verified against parental consent information.
For the purpose of the statistical analysis presented in this study, students were categorized into two groups:
– Active group: Participants reporting regular involvement in organized sports or structured physical activity (e.g., team sports, swimming, or martial arts) for at least one hour per week outside of the school’s mandatory physical education curriculum
– Non-active group: Participants who did not engage in any extracurricular structured physical activity.
While the prevalence of spinal deformities remains the primary focus of this study, these data were included to provide a preliminary sub-analysis of the cohort’s lifestyle characteristics. More granular data regarding specific sports types and intensity levels were collected for use in separate, specialized research papers.
Classification of scoliosis
In accordance with SOSORT screening guidelines and established clinical practices for school-based programmes [1, 9], participants who were screen-positive for trunk asymmetry (ATR 7° were further categorized into ‘structural’ or ‘postural’ types based on clinical flexibility tests.
Postural (functional) asymmetry: A finding was classified as ‘postural’ if the trunk rotation or rib hump fully or near- fully resolved during active postural correction, side-bending toward the convexity, or when the student was placed in a non- weight-bearing supine position. This indicated a lack of fixed vertebral rotation and a likely functional origin.
Structural asymmetry: A finding was classified as ‘structural’ if the rib hump and axial rotation remained fixed and did not reduce during these clinical manoeuvres, suggesting the presence of a permanent rotational deformity.
This clinical differentiation served solely as a screening- level triage to prioritize students for radiographic referral; however, it should be acknowledged that a definitive diagnosis of structural scoliosis requires radiographic confirmation (Cobb angle 10° and non-reducible vertebral rotation).
Results
The study included a total of 2,020 students between 10 and 15 years of age. The sample consisted of 1032 male students, representing 51.1% of the participants, and 988 female students, accounting for the remaining 48.9%. The age distribution of the participants was as follows: 10.8% were 10 years old, 29.9% were 11, 24.5% were 12, 20.1% were 13, 13.9% were 14, and 0.8% were 15.
The anthropometric characteristics of the cohort were as follows: the mean height was 155.44 ± 10.01 cm, the mean body weight was 50.35 ± 13.15 kg, and the mean body mass index (BMI) was 20.55 ± 4.35 kg/m2. These measurements provide a detailed anthropometric profile of the screened cohort of adolescents from nine public schools, representing a significant cross-section of the Tirana school-aged population during the peak years of spinal development.
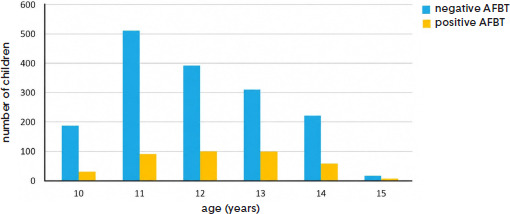
A total of 383 (19%) students had a positive AFBT. The prevalence of a positive AFBT was notably higher in female than in male students. Of the male students, 124 (12.01%) had a positive result, while 259 females (26.21%) were tested positive. The prevalence of a positive AFBT increased progressively with age from 10 to 13 years, representing a 1.64- fold increase over this period (Figure 3).
Figure 3
Distribution of positive and negative Adams Forward Bend Test (AFBT) results among children aged 10 to 15 years
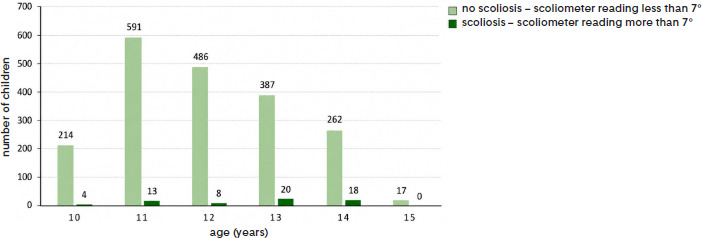
Of the 2,020 students screened, 63 (3.1%) were screen- positive for significant trunk asymmetry (scoliometer reading 7°). This includes students with thoracic, lumbar, or both types of scoliosis. A total of 15.93% of the students who had a positive AFBT also had a scoliometer reading above 7° (Figure 4). The prevalence of screen-positive trunk asymmetry was higher in female (4.11%) than male (2.38%) students. The prevalence also varied by age, peaking at the age of 14 (6.87%) and 13 (5.17%). Students who did not participate in sports had a higher prevalence of scoliosis.
Figure 4
A breakdown of the number of students with scoliosis with a scoliometer reading of 7° or higher
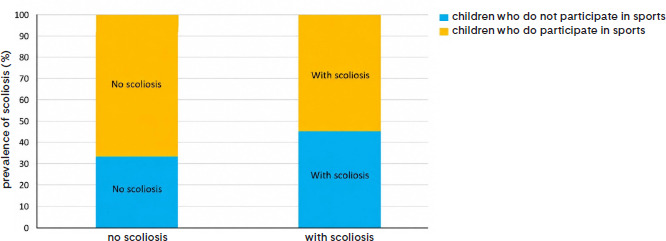
The analysis revealed a higher prevalence of screen-positive trunk asymmetry among children who did not participate in sports compared to their physically active peers. Specifically, 29 out of the 677 non-sport participants (4.47%) were identified with screen-positive trunk asymmetry, whereas 34 out of 1,343 children engaged in sports (2.60%) were affected (Figure 5). These findings suggest an inverse association between participation in sports and the prevalence of scoliosis, highlighting the potential protective role of regular physical activity.
Figure 5
Prevalence of scoliosis among children who did not participate in sports compared to their physically active peers
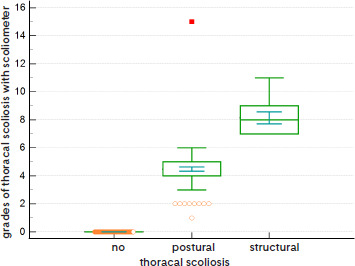
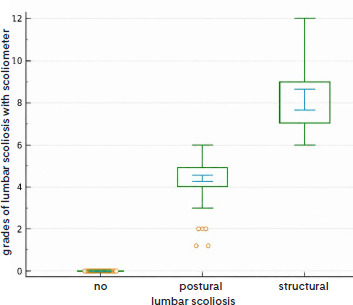
A total of 303 students (15%) were found to have thoracic scoliosis. Of these, 265 students had postural scoliosis (13.1%), while 38 had structural scoliosis (1.9%). The most common direction of the curvature in thoracic scoliosis was thoracic convexity dexter (10.3%). This type was more prevalent in female students, with 165 (16.7%) having postural thoracic scoliosis and 27 (2.73%) having structural thoracic scoliosis (Figure 6). Among male students, 100 (9.68%) had postural and 11 (1.06%) had structural thoracic scoliosis. Furthermore, A total of 204 students (10.1%) had lumbar scoliosis, with 167 (8.3%) being postural and 37 (1.8%) being structural type scoliosis (Figure 7).
Of the total students, 51 (2.5%) had either thoracic or lumbar scoliosis, while 12 students (0.6%) had both thoracic and lumbar scoliosis. The most common direction of the lumbar curvature was convexity dexter (5.65%).
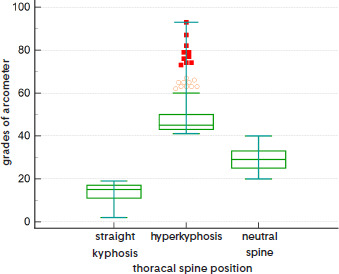
The study also identified cases of hyperkyphosis, which is defined as a thoracic curvature exceeding 40°. A total of 301 students (14.9%) were found to have thoracic hyperkyphosis. The mean thoracic curvature for these students was 47.81° (± 8.23°), with a range from 41° to 93° (Figure 8). In contrast, 1,454 students (71.98%) had a normal thoracic curvature, with a mean of 29.04° (± 5.33°).
Discussion
The findings of this school-based screening program in Tirana, Albania, reveal a significant prevalence of spinal deformities among the adolescent population, which is consistent with global epidemiological data. The overall prevalence of a positive AFBT was 19% [9, 22], and the prevalence of a scoliometer reading of 7° – the threshold for a positive scoliosis finding and referral for radiographic evaluation – was 3.1% [23, 24]. These results fall within the widely accepted prevalence range of 0.47% to 5.2% for AIS reported in international literature [3, 4, 28].
Our study results confirm a higher prevalence of screen- positive trunk asymmetry in female compared to male students, with females showing a prevalence of 4.11% and males 2.38%. This sex-based disparity is consistent with the epidemiological pattern well-documented in AIS [30–32]. Studies from different countries, including a large-scale screening survey in Turkey, found an AIS prevalence of 3.1% in females and 1.5% in males [34], while a study in Brazil reported respective prevalence rates at 2.2% and 0.5% [7]. These findings align with previous observations showing that the female- to-male ratio increases significantly with curve severity.
The prevalence of a positive AFBT and screen-positive trunk asymmetry varied with age, peaking at 13 and 14 years. Specifically, the prevalence of a positive AFBT was highest at age 13 (24.07%). This finding is consistent with previous research indicating that the pubertal growth spurt represents a period of peak risk for the onset and progression of spinal deformities [15, 35]. A study conducted in the state of São Paulo, Brazil, similarly identified a higher prevalence of AIS in the 13- to 14-year age group [7].
Furthermore, our study results indicate that students who did not participate in sports had a higher prevalence of screen- positive trunk asymmetry (4.47%) compared to those who participated in sports (2.60%). This finding is consistent with previous studies suggesting a relationship between physical activity and spinal health. Some studies have proposed that insufficient moderate/vigorous physical activity may adversely affect bone health and muscle function, which are considered risk factors for AIS [36, 37]. Conversely, certain competitive sports, such as gymnastics and artistic dance, have been associated with a higher risk of scoliosis development due to repetitive asymmetric movements [36, 38]. However, a general increase in physical activity is often considered protective [37, 39]. This finding suggests that promoting physical activity could be a valuable preventive measure in this population [40].
The use of a scoliometer in scoliosis screening is a widely accepted practice, with an ATR threshold of 7° commonly used as the criterion for referral [24–26]. Although less precise than full-spine radiography, the scoliometer represents a practical, non-invasive instrument suitable for large-scale school-based screening programmes. The effectiveness of these programmes has been a subject of ongoing debate, as they have been shown to identify a proportion of children who subsequently require treatment, while also yielding a substantial number of referrals that do not result in therapeutic intervention [8, 11, 12]. Nonetheless, recent evidence supporting the efficacy of bracing in mitigating curve progression underscores the continued clinical relevance of early detection [41]. In this context, the findings of the present study highlight the importance of sustained vigilance through structured screening initiatives to facilitate the timely identification and management of spinal deformities in the adolescent population.
Our study identified a high prevalence of screen-positive thoracic hyperkyphosis ( 40°) in 14.9% of the students, with a mean curvature of 47.81°. This finding warrants further considerations, as AIS is frequently associated with a reduction in the normal sagittal curvature, known as thoracic hypokyphosis, which can affect overall spinal balance [42]. The predominance of hyperkyphosis in our cohort suggests may have two possible explanations. First, it may reflect a true prevalence of postural or Scheuermann’s kyphosis in the general school population, which often co-exists with, but is etiologically distinct from, AIS [43, 44]. Second, it is important to acknowledge that the majority of our spinal positive findings were categorized as postural (functional) deformities, which are more readily influenced by habitual slumped posture that would present as hyperkyphosis. The non-invasive nature of the D’Osualdo arcometer, while suitable for large-scale screening, provides less precises assessment than radiographic evaluation and is known to be sensitive to small changes in patient positioning [27–29]. Therefore, the high prevalence of hyperkyphosis may reflect a high rate of non- structural postural issues in this adolescent population rather than a deviation from the typical spinal profile of true structural scoliosis.
In this study, basic anthropometric data (body height, body weight, and BMI) were collected to provide a comprehensive profile of the participant cohort. While a higher BMI can theoretically influence the accuracy of scoliometer readings – either by obscuring the rib hump or through asymmetrical fat distribution – our observations did not indicate a clear clinical correlation between BMI and the identification of significant trunk asymmetry [45, 46]. Within the assessed population, the distribution of screen-positive findings (ATR 7°) appeared relatively uniform across different body compositions. These observations suggest that the ATR 7° threshold remained a practical and consistent indicator for referral in this school-aged cohort, despite variations in individual anthropometric characteristics.
Limitations
This study has certain limitations that should be acknowledged. First, its cross-sectional design does not allow for causal inferences or the monitoring of curve progression over time. Second, although the AFBT, scoliometer, and arcometer are widely accepted screening instruments, they are inherently less precise than radiographic imaging, which remains the gold standard for the definitive diagnosis of scoliosis and other spinal deformities. Third, the study population was restricted to students attending public schools in Tirana, which may restrict the generalisability of the findings to other regions of Albania or to students attending private educational institutions. Finally, although body mass was measured, it was not included in the present analysis, and other potential confounding variables, such as family history and lifestyle habits, were not assessed, which may have influenced the prevalence estimates.
Despite these limitations, this study provides the first large- scale epidemiological data on the prevalence of scoliosis and spinal deformities among schoolchildren in Albania and thus makes an important contribution to the international body of evidence on adolescent spinal health.
Conclusions
This study provides the first large-scale population-based epidemiological data on the prevalence of scoliosis and spinal deformities in schoolchildren in Tirana, Albania. The results confirm a notable prevalence of positive screening findings, particularly among females and adolescents aged 13–14 years, mirroring international patterns. Importantly, the inverse association observed between participation in sports and scoliosis prevalence highlights the potential preventive role of physical activity.
These findings underscore the importance of school-based screening programmes as a public health strategy for early detection and timely management of spinal deformities in adolescents. Implementation of such programmes, alongside health education and physical activity promotion, could play a crucial role in preventing progression to more severe conditions and reducing the long-term burden of spinal deformities in Albania.

