

Introduction
Lumbar disc herniation is a common spinal disorder and is a major contributor to low back pain (LBP) and radiculopathy, negatively affecting functional capacity and quality of life (QOL) [1]. Lumbar discectomy is a surgical intervention of choice for patients who fail to respond to conservative treatment, especially when neurological symptoms and significant disability are present [2]. The primary objective of lumbar discectomy surgery is to release the pressure on the nerve caused by a prolapsed disc and restore the neurological function [2]. Lumbar discectomy, a motion-preserving surgery, effectively relieves lumbar radicular pain in 80–90% of patients and has remained widely performed since its popularisation in 1934 [3]. The incidence of operated lumbar disc herniations was 0.5/1000 per year in men and 0.4/1000 per year in women, rising to 0.8 and 0.6/1000, respectively, among those aged 20–64 [4].
Although the lumbar discectomy is usually effective in solving leg pain and radicular symptoms, the process does not widely address biomechanical and neuromuscular deficits that often occur [5]. Many patients experience residual pain, segmented instability, muscle weakness, and psychological issues, which can all have a negative effect on functional recovery and affect long-term results negatively [6]. These sequelae highlight the need for rehabilitation strategies aimed at restoring functional abilities and improving the overall physical and mental aspects of recovery.
The physiotherapy programs have been shown to reduce postoperative complications and accelerate recovery by incorporating supervised and progressive exercise programs [7]. Supervised physiotherapy refers to structured exercise sessions under the guidance of a physiotherapist, allowing real-time correction, progression, and adherence monitoring, whereas unsupervised or home-based programs rely on patients to carry out exercises independently with minimal oversight [8].
Several studies in musculoskeletal rehabilitation show that supervised programs lead to greater gains in pain reduction, physical function, and patient adherence than unsupervised ones [8]. However, in lumbar disc surgery, evidence is mixed: a Cochrane review and randomised trials have found no significant differences between supervised and home exercise in pain and disability outcomes post-discectomy [9], while more recent reviews suggest supervised interventions may provide added benefits in quality of life and self-efficacy after lumbar spine surgery [10].
Exercise-based rehabilitation improves spinal stability, facilitates neuromuscular control, and increases physical performance [11]. Evidence suggests that the initial active rehabilitation post-lumbar discectomy is linked with better patient satisfaction, faster return to work, and improved functional results compared to delayed and passive rehabilitation protocols post-lumbar discectomy [7].
In addition, the multidimensional burden of lumbar spinal disorders is often beyond physical problems [7]. Psychological factors, especially anxiety and depression, are often reported in patients undergoing spinal surgery and have been shown to adversely affect postoperative recovery [12]. Despite the biopsychological nature of pain, the impact of physiotherapy intervention on the consequences of mental health in this population remains poorly documented.
From a clinical point of view, integration of physical and psychological domains in postoperative care can improve outcomes and align with contemporary, patient-centred approaches for rehabilitation. Physiotherapy programs that are both evidence-based and favourable for individual patient profiles are required to ensure the highest standards of care. In light of these ideas, the purpose of this study is to evaluate the effects of the physiotherapy exercise program on the quality of life, pain, functional disability, anxiety, and depression in patients post-lumbar discectomy.
Despite the evidence supporting the role of rehabilitation, there remains limited knowledge regarding the comprehensive effects of supervised physiotherapy programs on both physical and psychological outcomes following lumbar discectomy. Existing studies have primarily focused on pain and functional outcomes, with less attention given to quality of life, anxiety, and depression. This gap highlights the need to evaluate physiotherapy interventions that address both physical and psychosocial recovery in this patient population. Therefore, the purpose of this study was to evaluate the effects of a supervised physiotherapy exercise program on quality of life, pain, functional disability, anxiety, and depression in patients following lumbar discectomy.
Subjects and methods
Design
This study was conducted as part of a master’s thesis and received approval from the Research Committee of the College.
The proposed trial was a Quasi-Experimental Study, in which patients were unaware of their group allocation. Baseline data were collected before the intervention, with post-intervention data gathered at 6 weeks and follow-up at 4 weeks.
Sample size calculation
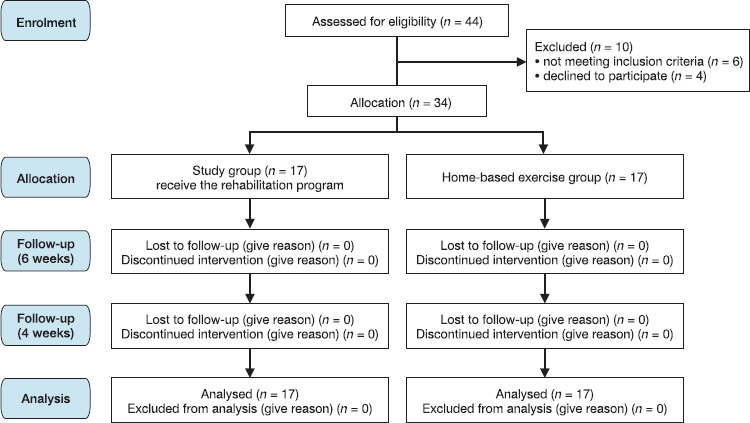
The number of patients (n = 28) was determined using Software G. Power 3.1.9.2 entering data of changes in SF-36 scores, in which the effect of physiotherapy intervention was examined on the QoL in patients post-lumbar discectomy, and revealed an effect size of 1.17 [13]. Based on these effect estimates, a sample size of 28 patients was found to be essential at an alpha of 0.05 and a power of 90% to test the present hypothesis. With an expected dropout of 20%, the total sample was 34 patients, 17 in each group. Around 15–20 patients undergo a lumbar discectomy monthly in Al Shift Hospital [13]. All participants completed the study, and no dropouts or losses to follow-up occurred. Therefore, no specific strategies for handling missing data were required. Sample size was calculated using the Short Form-36 (SF-36) questionnaire.
Randomization
A total of 34 patients were randomised using simple block randomisation with a block size of four to ensure balanced allocation across the study groups. In this method, every block of four participants was distributed equally between the two groups (e.g., two patients per group in each block), preventing imbalances that could arise if randomisation was performed without restriction. Single blinding was applied: participants were unaware of their group allocation. Block randomisation was implemented with consideration of sex to ensure an equal distribution of males and females between the two groups.
Eligibility criteria
Patients were included if they were male or female, had undergone a first-time lumbar discectomy, had a score > 7 on the Hospital Anxiety and Depression Scale (HADS), and were aged 18–55 years. They were excluded if they had a recent surgery, patients who had physiotherapy intervention before the study, the presence of co-morbidity, including spondylarthritis, joint disease, and systemic or heart disease, multiple- level discectomy, any other associated problems like bone infection or neurological problems, or those who were unwilling to participate. Patients were also excluded if they were currently using medication for chronic diseases (e.g., diabetes, cardiovascular, or neurological conditions), and medications that could influence mental health status (e.g., antidepressants, anxiolytics) or sleep quality (e.g., hypnotics, sedatives).
Ethical considerations
Confidentiality was ensured by anonymising the collected data, which were stored securely and used solely for research purposes. No personal identifiers were disclosed in any part of the study. The study was conducted in accordance with the CONSORT (Consolidated Standards of Reporting Trials) guidelines [14], and the principles of the Declaration of Helsinki [15].
The study upheld beneficence by maximising benefits while minimising harms. Participants, post-lumbar discectomy for nerve root compression, received a non-invasive supervised exercise program to enhance recovery, building on standard care. Direct benefits included significant improvements in quality of life (SF-36), pain (Visual Analogue Scale, VAS), disability (Oswestry Disability Index, ODI), and anxiety/depression (HADS), with greater gains in the supervised group. The home-based exercise group received standard advice, ensuring equipoise. Societal benefits include evidence for integrating physiotherapy into post-discectomy care, potentially reducing chronic disability and pain.
Specify source and recruitment setting
Participants were recruited from Al Shifa Hospital in the Neurosurgery Department. Eligible patients who met the inclusion criteria were invited to participate during their routine visits, and those who agreed provided written informed consent.
Intervention
Supervised group
Participants in the supervised group underwent a progressive physiotherapy program starting 48 hours post-surgery and continuing for six weeks, with three supervised sessions per week. During the early postoperative phase (weeks 1–2), exercises focused on low-intensity, pain-free movements including pelvic tilts, diaphragmatic breathing, abdominal and thigh isometrics, and quadriceps strengthening, with gradual progression in repetitions based on patient tolerance. In the intermediate phase (weeks 3–4), moderate-intensity exercises were introduced, including back stretches, straight leg raises, hamstring and hip flexor stretches, isotonic quadriceps strengthening, and early motor control training. The late/ post-acute phase (weeks 5–6) emphasised strengthening, mobilisation, and functional exercises within safe pain-free limits, with intensity gradually increased according to patient feedback and functional tolerance. Throughout the program, therapists supervised all sessions to ensure correct technique, posture, breathing, muscle recruitment, and safety [16] (Table 1).
Table 1
Characteristics of the postoperative physiotherapy program
Home-based exercise group
Participants received a single educational session immediately post-surgery, during which the physiotherapist provided oral instructions and general advice. These instructions included guidance on safe movements and postural precautions, gradual resumption of daily activities, basic range-of-motion and gentle mobility exercises for the lower back and lower limbs, ergonomic advice for sitting, sleeping, and lifting, and information on pain management and activity pacing. This approach aligns with previously reported rehabilitation protocols in lumbar surgery [17].
On non-clinic days, patients continued their prescribed home exercises, with adherence monitored through exercise logs and weekly therapist follow-ups. This method is consistent with studies that have utilised home exercise programs to manage postoperative recovery in lumbar surgery patients [18]. Participants in the home-based exercise group did not receive any heat or cold therapy.
Safety monitoring
Participants were closely monitored throughout the study for any adverse events or side effects related to the interventions. Minor events, such as temporary muscle soreness or mild fatigue, were documented in patient logs by the supervising physiotherapist. Any unexpected or serious events would have been reported immediately to the study team. This monitoring ensured participant safety and adherence to the intervention protocol.
Adverse events
In this Quasi-Experimental Study, no serious adverse events were reported in either the supervised physiotherapy group or the home-based exercise group throughout the 6-week intervention and 4-week follow-up periods. Minor, transient side effects consistent with early postoperative recovery and low-intensity exercise were observed, including temporary muscle soreness (n = 3 in the supervised group; n = 2 in the home-based group) and mild fatigue (n = 3). These events occurred primarily during the first two weeks of the intervention, were mild in severity, resolved spontaneously without intervention, and did not lead to study discontinuation. All adverse events were considered likely related to the exercise intervention rather than surgery. Occurrences were monitored and recorded by the supervising physiotherapist in patient logs, and the incidence was comparable between groups, indicating that the intervention was safe.
Evaluation procedures
Visual Analogue Scale
The Visual Analogue Scale (VAS) is a validated self-rating scale for acute and chronic pain. Scores are marked on a 10-cm line that represents a continuum from no pain (0) to worst pain (10) [19]. The VAS is a reliable scale, and it showed a moderate to strong correlation for validity in pain measurement [20]. It has demonstrated excellent test-re-test reliability (ICC = 0.97) and good construct validity, correlating strongly with other pain assessment instruments such as the Numeric Rating Scale and the McGill Pain Questionnaire [21].
Oswestry Disability Index
The Oswestry Disability Index (ODI) is a tool widely utilised in clinical practice and research to measure disability for patients suffering from low back pain. The self-administered questionnaire includes 10 categories regarding pain, lifting, personal care, walking, sitting, sexual life, standing, social life, sleep, and travel. The ODI provides 6 statements per item. The patient then selects the sentence that most closely matches their experience. Each response has a score in the range 0–5, where one represents the first statement and five the last. A score of zero shows minimum disability. The total score ranges between 0 to 100, where 0 is equated with no disability, and 100 is the maximum disability [22]. It demonstrates excellent internal consistency (Cronbach’s = 0.87–0.95) and test-retest reliability (intraclass correlation coefficient, ICC = 0.80–0.99), and has shown good construct validity, correlating strongly with other measures of pain and functional impairment. These psychometric properties support its use as a reliable and valid tool for evaluating disability in patients post-lumbar discectomy [23].
Short Form-36
It is a self-assessment scale with a 36-item, 8-scale questionnaire. Physical functioning, pain, role limitations, vitality, social functioning, mental health, and overall health status are all covered in the measure. Every scale has a score ranging from 0 to 100, where 0 denotes the lowest quality of life and 100 denotes the highest quality of life. Each scale’s score is determined separately. Physical functioning (PF), role physical (RP), bodily pain (BP), general health (GH), vitality (VT), social functioning (SF), role emotional (RE), and mental health (MH) are the eight scales that the SF-36 measures. The SF-36 measured two different items, according to component analyses: a mental dimension, represented by the Mental Component Summary (MCS), and a physical dimension, represented by the Physical Component Summary (PCS). The proportions of each scale’s contribution to the PCS and MCS measure scores vary [24]. It is reliable and valid. The Cronbach’s alpha for SF-36 was 0.85, and it is reliability coefficient greater than 0.75 [25].
Hospital Anxiety and Depression Scale
Patients’ levels of anxiety and depression were evaluated using the Hospital Anxiety and Depression Scale (HADS). The HADS is a 14-item scale comprising seven items for each of the anxiety and depression subscales. Each item is scored on a four-point scale from 0 to 3, where 3 represents the highest level of anxiety or depression. Subscale scores are classified as normal (0–7), mild (8–10), moderate (11–15), and severe (16–21) [26]. It was developed to provide clinicians with a reliable, valid, and practical tool to assess anxiety and depression in medical patients [27]. It demonstrates good internal consistency (Cronbach’s = 0.80–0.93) and construct validity, with scores correlating well with other established measures of anxiety and depression [28].
Statistical analysis
Data were analysed using IBM SPSS Statistics 27 (USA). Descriptive statistics (mean ± SD for continuous variables and frequency/percentage for categorical variables) were calculated to summarise participant characteristics. The assumptions for parametric tests were evaluated prior to analysis. Normality was confirmed using Shapiro–Wilk test and visual inspection of histograms, and homoscedasticity was verified through examination of baseline variances across groups, indicating that parametric tests were appropriate. Homoscedasticity was assessed using Levene’s test for equality of variances. Both assessments confirmed that the assumptions for parametric tests.
Independent samples t-test was used to compare baseline continuous variables between the two groups. Repeated- measures ANOVA was used to assess within and between- group differences over time. The factor time in the repeated measures ANOVA referred to the three evaluation points: baseline, post-intervention, and follow-up. Post hoc analyses with Bonferroni adjustment were performed to identify pairwise differences between time points.
Results
Baseline group characteristics
Table 2 presents the baseline demographic and clinical characteristics of participants in the supervised physiotherapy group and the home-based exercise group. No statistically significant differences were observed between the groups in age, gender distribution, pain intensity, disability, anxiety, depression, or most SF-36 subscales, indicating that both groups were comparable prior to the intervention (p > 0.05). Gender distribution was nearly equal between the two groups, with 9 males (52.9%) and 8 females (47.1%) in the supervised physiotherapy group, and 8 males (47.1%) and 9 females (52.9%) in the home-based exercise group.
Table 2
Characteristics of the study participants
Table 3 presents the mean and standard deviation (SD) values of all study outcomes for both the supervised physiotherapy and home-based exercise groups at three assessment points: baseline (pre-intervention), after six weeks of physiotherapy, and at the four-week follow-up. The results of the repeated measures ANOVA for within-subjects (time), interaction (time × group), and between-groups effects are summarized in Table 4, while Table 5 presents post-hoc pairwise comparisons with Bonferroni adjustment. The study flow is shown in Figure 1.
Table 3
Illustrate the changes in mean and SD of the study instruments for the supervised group and the home-based exercise group among patients post lumbar discectomy
Table 4
Results of repeated measures ANOVA for within-subjects and between-groups effects on study variables (time, time group, and groups)
Table 5
Post-hoc pairwise comparisons (Bonferroni) of the study instruments across time in home-based exercise and supervised groups
Post-hoc Bonferroni comparisons showed significant improvements across all outcomes within both groups over time. In the home-based exercise group, the largest changes from pre-test to follow-up were observed in general health (MD = −11.35), bodily pain (MD = −10.47), disability (MD = 19.10), anxiety (MD = 4.47), and depression (MD = 5.52). The supervised group demonstrated greater magnitudes of improvement across the same period, particularly for general health (MD = −16.23), physical function (MD = −16.00), bodily pain (MD = −16.06), disability (MD = 29.23), and mental health (MD = −11.06). Across most variables, the supervised group showed larger pre–post and pre–follow-up mean differences compared with the home-based group, indicating a stronger treatment effect. All significant comparisons were supported by adjusted p-values and 95% confidence intervals that did not cross zero (Table 5).
Effects of interventions on pain intensity
A significant main effect of time was found (p < 0.01, p2 = 0.94), indicating that pain intensity decreased significantly across all assessments. There was also a significant time × group interaction (p < 0.01, p2 = 0.29) and a significant between-group difference (p < 0.01, p2 = 0.48), showing that the supervised physiotherapy group achieved a greater reduction in pain than the home-based exercise group (Table 3). Post-hoc analysis (Table 4) confirmed significant improvements between baseline and post-intervention, and between baseline and follow-up in both groups, with larger mean differences observed in the supervised group.
Effects of interventions: disability
Significant effects were found for time (p < 0.01, p2 = 0.91), time × group (p < 0.01, p2 = 0.46), and between groups (p < 0.01, p2 = 0.56). These results indicate consistent improvement in disability levels in both groups, with superior outcomes in the supervised physiotherapy group (Table 3). Post-hoc pairwise comparisons demonstrated marked reductions from baseline to post-intervention and from baseline to follow-up in both groups (Table 4).
Effects of interventions on anxiety
The within-subjects effect of time was significant (p < 0.01, p2 = 0.77), indicating improvement in anxiety levels over time. Although the time × group interaction was not significant (p = 0.17), a significant between-group difference was found (p = 0.006, p2 = 0.21), suggesting that the supervised group had lower anxiety scores overall (Table 3). As shown in Table 4, anxiety decreased significantly from baseline to both post-intervention and follow-up assessments in both groups.
Effects of interventions on depression
Significant main effects were observed for time (p < 0.01, p2 = 0.92), time × group (p < 0.01, p2 = 0.22), and between groups (p < 0.01, p2 = 0.46) (Table 3). These findings demonstrate that depression levels improved across time, with greater improvement in the supervised group. Post-hoc results confirmed significant reductions from baseline to both post-intervention and follow-up within both groups.
Effects of interventions on health-related quality of life (SF-36 subscales)
General health
A significant time effect (p < 0.01, p2 = 0.78), interaction (p = 0.003, p2 = 0.19), and between-group difference (p = 0.03, p2 = 0.14) were found, indicating that both groups improved, with the supervised group showing greater enhancement. Pairwise comparisons (Table 4) revealed significant improvements across all intervals in both groups.
Physical functioning
The main effect of time was significant (p < 0.01, p2 = 0.59) and the time × group interaction was also significant (p = 0.018, p2 = 0.15), favouring the supervised group. Between-group differences were not significant (p = 0.5). Post-hoc results confirmed greater gains in physical function within the supervised group.
Role limitations (physical role)
A significant time effect was observed (p < 0.01, p2 = 0.55), while interaction and between-group differences were not significant. This suggests comparable improvement in both groups over time.
Bodily pain
Significant effects were found for time (p < 0.01, p2 = 0.75), time × group (p = 0.02, p2 = 0.15), and between groups (p < 0.01, p2 = 0.42). These results confirm that the supervised group experienced greater improvement in bodily pain perception.
Emotional role
Only the main effect of time was significant (p < 0.01, p2 = 0.74), indicating overall improvement in emotional well- being across both groups. No significant group effect or interaction was noted.
Mental health
A significant main effect of time (p < 0.01, p2 = 0.61), interaction (p = 0.02, p2 = 0.13), and between-group effect (p = 0.02, p2 = 0.16) was detected, showing greater mental health improvement in the supervised group.
Discussion
The present study investigated the impact of a supervised exercise program on quality of life, pain, disability, depression, and anxiety in individuals following lumbar discectomy. What sets this study apart is the early initiation of physiotherapy – commencing just 48 hours postoperatively – which is both safe and effective. The postoperative physiotherapy program implemented in this trial included gentle soft tissue mobilisation, core strengthening, motor control training, and stretching, providing a comprehensive approach that addresses both physical and psychological recovery. To our knowledge, few trials have simultaneously examined these multiple dimensions of postoperative recovery, making the findings particularly relevant for clinical practice and research. By demonstrating that early, structured physiotherapy can enhance physical function, reduce pain and disability, and improve psychological well-being, this study provides strong evidence supporting holistic rehabilitation strategies after lumbar discectomy.
The results showed a significant positive effect of the intervention across all measured outcomes, favouring the experimental group. These findings highlight the innovation of integrating early supervised physiotherapy into postoperative care, demonstrating that it can safely accelerate recovery while simultaneously improving both physical and mental health outcomes. This underscores the importance of early rehabilitation interventions not only for optimising functional recovery but also for promoting psychological resilience, potentially reducing the risk of chronic pain and long-term disability.
Quality of life
The results demonstrate a significant positive effect of the intervention on QoL, favouring the supervised group. The results align with the literature regarding the effects of early physical therapy on QoL postoperative lumbar discectomy. A previous study found significant improvements in QoL among patients receiving a combination of education and exercise [29]. Similarly, significant enhancements in general health and emotional role subscales among patients engaged in comprehensive physiotherapy programs [13]. The findings of the study are also similar to those of Harts and colleagues. In that study, greater increases in quality-of-life scores were obtained in a group that participated in a high- intensity lumbar extensor program, as compared with a control group [30]. The findings align with prior research showing that anxiety, emotional stability, and social support are key determinants of quality of life, emphasising the role of holistic rehabilitation approaches that target both physical and psychological outcomes [31]. Improvements in QoL may result from enhanced physical function, reduced pain, and increased self-efficacy during rehabilitation.
The study did not, however, find any variations in social functioning and vitality between intervention groups. This suggests that while exercise effectively targets physical and emotional domains, broader social and contextual factors may require additional psychosocial or multidisciplinary interventions. The trial demonstrates that exercise alone is sufficient to produce meaningful improvements in QoL dimensions.
Pain
The relationship between physiotherapy exercises post- surgery and long-term pain relief is well-documented [32]. Early physiotherapy programs are both safe and effective, leading to enhanced health tools [33]. Significant improvements in pain levels have been reported at various follow-up intervals, including 1 month, 3 months, 6 months, and 1 year post-surgery [34]. These findings are similar to our results, which showed a statistically significant reduction in pain levels in the supervised group compared to the home-based exercise group. Exercises have been shown to improve lumbar muscle strength, correct imbalances, and reduce pain [35]. In terms of musculoskeletal function, exercise enhances spinal stability, strengthens core muscles, and improves posture. This, in turn, reduces mechanical stress on the spine and alleviates pain. This leads to improved functional capacity and a decrease in disability [36]. Importantly, the magnitude of pain reduction exceeded the minimal clinically important difference (MCID) for the VAS (1.4 cm), indicating that the changes were not only statistically significant but also clinically meaningful [37]. The mechanisms underlying these improvements may include enhanced core stability, improved lumbar muscular endurance, and reduction of neural mechanosensitivity. Furthermore, exercise has been shown to modulate inflammatory pathways and central pain processing, which could explain the sustained reductions in pain intensity.
Disability
The study showed that the supervised group’s disability levels improved statistically significantly when compared to the home-based exercise group. This is consistent with earlier studies that have evaluated physiotherapy therapies in postoperative populations. A previous study found similar results, indicating that a combination of physiotherapy exercises and advice led to significant reductions in the level of disability post lumbar discectomy [38]. Contrastingly, other studies reported non-significant improvements in disability levels, potentially due to differences in intervention duration, type of exercise, frequency, or intensity [39, 40]. For disability measured by the ODI, the supervised group showed substantial improvement, with mean scores decreasing from 82.6 at baseline to 58.5 post-intervention and 53.4 at follow-up. The home-based exercise group demonstrated smaller improvements. The observed mean changes exceeded the MCID of 7–51 points, indicating clinically meaningful improvements in disability, particularly in the supervised group [41]. Such variability across studies may highlight the importance of tailoring exercise protocols in terms of intensity, duration, and frequency to optimize functional outcomes.
Depression and anxiety
A key strength of this study lies in addressing both physical and psychological domains of recovery, which are often considered separately in postoperative care. In addition, the results concerning the psychological factors of recovery showed more significant improvements in depression and anxiety among patients in the supervised group compared to the home-based exercise group. Although this topic remains underexplored, the results are consistent with previous research showing that exercise regimens can improve psychological well-being [42]. The encouraging environment and clear instructions during supervised physical therapy sessions may have been crucial in decreasing anxiety and depressive symptoms. Consistent with prior research in chronic low back pain populations, psychological factors such as anxiety, emotional stability, and social support significantly influence quality of life [43]. This aligns with the findings where targeted physiotherapy not only improved the physical component but also led to clinically meaningful reductions in anxiety and depression, highlighting the importance of addressing both physical and psychological domains in postoperative recovery
For mental health, the supervised group demonstrated marked reductions in anxiety and depression scores. Anxiety scores (HADS-A) decreased from 10.2 ± 1.07 at baseline to 6.8 ± 1.81 post-intervention and 5.8 ± 0.95 at follow-up, while depression scores (HADS-D) decreased from 11.3 ± 0.85 to 6.5 ± 0.94 and 5.7 ± 1.0, respectively. The home-based exercise group showed smaller improvements (HADS-A: 10.8 ± 0.97 to 8.4 ± 1.58 to 6.3 ± 1.36; HADS-D: 11.1 ± 0.85 to 8.2 ± 1.1 to 6.8 ± 1.2). These changes exceed the established MCID for HADS scores reported in the literature: 3.8 points for HADS-A and 3.3 points for HADS-D from baseline to final assessment [44]. Thus, the improvements observed in the supervised group represent clinically meaningful reductions in anxiety and depression symptoms, supporting the effectiveness of the supervised physiotherapy intervention
Engaging in regular physical activity stimulates the release of endorphins and other neurotransmitters such as serotonin and dopamine, which are associated with improved mood and reduced symptoms of depression and anxiety [45]. Furthermore, exercise has been associated with improved sleep quality and reduced fatigue, contributing to overall better health in post-surgical patients [45]. Collectively, these physiological mechanisms underscore the importance of incorporating exercise into rehabilitation programs for patients recovering from lumbar discectomy, as it addresses both the physical and psychological aspects of recovery.
The intervention is aimed at addressing physical and psychological issues, such as depression and anxiety, which are often overlooked in postoperative care. This approach is essential, as overall rehabilitation depends on psychological well- being. Although the results are in line with previous research, they also show that more studies are necessary to determine the best ways to optimise the advantages of early physiotherapy interventions and to investigate the processes by which these exercises enhance psychological factors and overall quality of life [46].
The supervised physiotherapy program was feasible and well-tolerated by all participants. Adherence to the intervention was high, with all scheduled sessions completed as planned. No adverse events, complications, or exacerbations of symptoms were reported during or after the intervention, indicating that the program is safe for post-lumbar discectomy patients. These findings support the practical applicability of the exercise program in clinical settings.
Comparative advantages of supervised vs. unsupervised exercise
An important consideration highlighted by our findings is the comparative advantage of supervised physiotherapy over home-based, unsupervised exercise programs. Supervised sessions provide real-time guidance, ensuring correct technique, optimal exercise intensity, and progression, which enhances the safety and effectiveness of the intervention. Furthermore, supervised programs foster a strong therapeutic alliance between the patient and physiotherapist, which can improve motivation, adherence, and patient confidence – factors that are more difficult to achieve in unsupervised settings.
While supervised programs may be associated with higher initial costs and resource demands, the potential for accelerated recovery, reduced complications, and prevention of chronic disability may offset these expenditures, making them cost-effective in the long term. From a feasibility perspective, structured protocols that combine in-person supervision with remote follow-up or digital support could further enhance accessibility and adherence, particularly for patients with logistical or mobility constraints.
Future refinements to the supervised model could include tailored exercise progression based on patient-specific outcomes, integration of motivational strategies, and incorporation of telehealth sessions to maintain continuity of care while optimising resource utilisation. These considerations suggest that supervised physiotherapy not only maximises clinical benefits but also provides a flexible framework adaptable to diverse healthcare settings.
Clinical value and implications
The findings of this study have important clinical implications for postoperative care following lumbar discectomy. The supervised physiotherapy program not only reduced pain and disability but also improved psychological well-being, demonstrating that early, supervised rehabilitation can produce clinically meaningful benefits across multiple domains. Clinicians can incorporate such exercise programs into standard postoperative protocols to optimise functional recovery, enhance quality of life, and potentially reduce the risk of chronic pain and long-term disability. Furthermore, addressing both physical and psychological aspects highlights the importance of a holistic rehabilitation approach, suggesting that integrating tailored care and mental health support into physiotherapy programs can maximise patient recovery and satisfaction. These results support the adoption of evidence-based, early exercise interventions as a standard component of postoperative management in lumbar discectomy patients.
Limitations
Nevertheless, several limitations must be acknowledged, including the relatively small sample size, lack of therapist blinding, and absence of long-term follow-up beyond six months, and absence of prospective registration in a clinical trial database. These factors may limit the generalisability of the findings. Additionally, the use of self-reported measures increases the risk of response bias, which might compromise the reliability of the findings. Future studies should attempt to navigate around these limitations by using larger, more varied samples and longer follow-up periods in order to better understand the effects of physiotherapy interventions.
Scope and future directions
This study provides evidence that early, supervised postoperative physiotherapy can safely and effectively improve both physical and psychological outcomes, including pain, disability, quality of life, anxiety, and depression, following lumbar discectomy. The intervention was feasible, well-tolerated, and showed high adherence, supporting its practical applicability in clinical settings.
Future research should investigate the long-term effects of postoperative physiotherapy using larger sample sizes and longer follow-up periods, optimise exercise type, intensity, and duration, and evaluate multidisciplinary approaches that target broader psychosocial factors, including social support and emotional well-being, to further refine rehabilitation protocols and promote holistic patient care.
Conclusions
This study demonstrates that a supervised, early postoperative physiotherapy program, initiated safely 48 hours after lumbar discectomy, leads to significant and clinically meaningful improvements in pain, disability, quality of life, and psychological well-being. The findings directly address the research questions, confirming that supervised exercise interventions are more effective than standard care in enhancing both physical and mental recovery. By integrating core strengthening, motor control training, and patient-centred guidance, the intervention provides a holistic approach that supports optimal functional and psychological health. These results underscore the importance of early, evidence-based physiotherapy as a standard component of postoperative care, with implications for improving recovery trajectories and long-term patient outcomes.

