

Introduction
Obesity is characterised by the excessive and abnormal accumulation of fat in the body [1], with body mass index (BMI) values of 25 kg/m2 or higher in Asian populations as they typically have a higher proportion of body fat and BMI compared to Western population [2, 3]. It constitutes a significant public health challenge in the twenty-first century, as it increases the risk of developing numerous medical conditions including physical and neurocognitive impairments [4].
Higher BMI has been found to correspond to greater postural instability [5], which refers to an impaired ability to maintain a state of equilibrium in response to external or volitional perturbations of the postural control system [6].
Several possible pathways that explain how obesity affects postural control have been established. An important contributing aspect is the elevated ankle torque brought on by an anterior shift in the centre of mass, which modifies the dynamics of balance. Obesity has also been linked to increased motor command variability, which may have an impact on the accuracy and consistency of postural adjustments [7]. The diminished sensitivity of mechanoreceptors on the plantar surface, which hinders the body’s capacity to recognise and react to minute variations in posture [8, 9], ultimately leads to impaired balance in obese individuals [10].
Furthermore, it appears that postural instability may occur during dual-task (DT) conditions when attentional demands are higher, especially among individuals with obesity, who often exhibit altered executive function, thereby increasing the fall risk [11]. Obesity has also been increasingly associated with detrimental neurocognitive consequences, such as diminished cognitive capacity, particularly in regard to frontal lobe executive functions [12]. Obesity impacts the central nervous system in a variety of ways, including molecular changes like insulin resistance, oxidative stress, hormone imbalance, and neuroinflammation, as well as structural alterations like brain atrophy [13].
Thus, this study addresses a critical gap in the literature by examining the efficacy of DT training, attentional prioritisation strategies, and their interaction with obesity-related executive dysfunction in improving postural stability. The findings have the potential to inform evidence-based interventions aimed at reducing fall risk and improving functional outcomes in this high-risk population.
Therefore, this study’s primary objective is to investigate and compare the effects of DT training and single-task (ST) training on postural stability in adults with obesity. Additionally, we aim to evaluate the influence of fixed-priority and variable-priority DT interventions on postural stability and balance in obese individuals.
Subjects and methods
Design
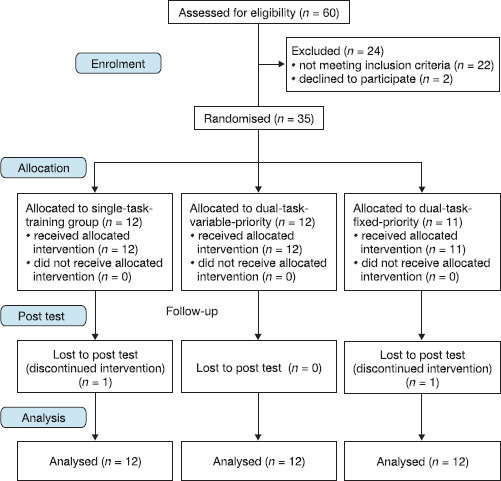
The study was designed as a three-arm parallel group, randomised controlled trial. The study was carried out according to the recommendations of CONSORT guidelines for randomised studies (Figure 1).
Participants
Participants included in the study had a BMI ranging from 25 to 39.9 kg/m2, were between 30 and 60 years of age, and had a waist–hip ratio of 0.85 in males and 0.80 in females. Inclusion criteria also required a unipedal stance test score 20 s on the dominant side, and the Mini Mental State Examination (MMSE) score > 24. Participants were excluded if they reported any neurological conditions such as stroke, multiple sclerosis or neuropathy, recent lower extremity injury/ trauma/surgery in the past 6 months, lower extremity total joint replacement, uncorrected vision problems, inability to walk independently, uncontrolled diabetes, or known cardiovascular disease.
Sample size
The number of subjects for this study was determined using the G*Power 3.1 software, following statistical parameters derived from a previous study by [14]. The calculations were based on an effect size of 0.72, a significance alpha level of 0.05, and a statistical power (1-beta) of 0.80. The analysis indicated that a minimum of 29 participants would be required to achieve sufficient statistical power. However, to account for the possibility of participant dropout, which was estimated at 20%, the final sample size was increased to 35 to ensure the study’s reliability and validity.
Randomisation and allocation
Block randomisation was implemented using the Sealed Envelope randomisation program (sealedenvelope.com) to ensure balanced allocation of participants across study groups. Allocation concealment was maintained throughout the randomisation process. Additionally, single-blinding was ensured by keeping participants unaware of the treatment they received.
Assessment and outcome measure
At baseline, height, weight, BMI, waist circumference, hip circumference, waist–hip ratio, and MMSE and unipedal stance test were recorded for the screening process. A calibrated stadiometer, weighing machine, and measuring tape were used to record the height, weight, and circumference, respectively. Evaluation was performed before and after the treatment for all variables. Primary outcome measurement included postural stability, measured through a Pedalo®-Sensamove balance device, and secondary outcome measures included Berg balance scale, TUG, TUG-Cog and unipedal stance test (UST).
Postural stability
Postural stability – This was evaluated using the Pedalo®- Sensamove balance device. It included CoP sway, CoP range, and reaction time. To measure the CoP sway (forward, backward, left and right), the subjects were asked to stand on the balance board while keeping their hands on their pelvis with their eyes open (EO) fixating their vision on the screen for 30 s, then in the eyes closed (EC) condition.
The CoP range was calculated by instructing the subjects to move in four different directions (forward, backward, left, and right) and to hold the position for 3 s in each direction, and the ranges were recorded.
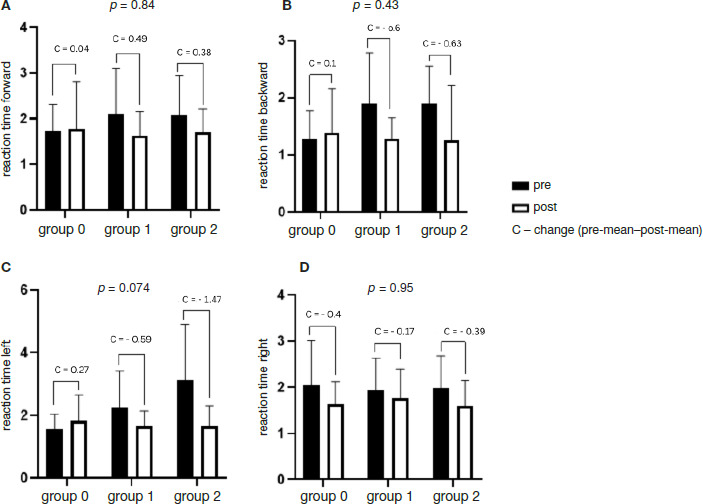
Reaction time – Participants were instructed to stand on the balance board while a screen was placed in front of them. The objective for the participants was to touch the coloured spot on the screen as soon as it appeared, ensuring their centre of pressure (CoP) was aligned. The reaction time was determined as the duration taken for the participant to complete the task. The measurement of reaction time was conducted individually in four specific directions: forward, backward, right, and left [15].
TUG and TUG-Cog
TUG – the subjects were instructed to get out of a chair, walk three metres at a comfortable pace, turn around a cone, get back in the chair, and then sit down. The amount of time needed to finish the test was noted. TUG is a good indicator of physical performance in the obese population [16].
TUG-Cog – the subjects were instructed to get out of a chair, walk for three metres at a comfortable pace, turn around a cone, get back in the chair, and then sit down while counting backwards by threes from a random number between 20 and 100. The amount of time needed to finish the test was noted. TUG-Cog has good reliability in older adults, and the average time to perform TUG-Cog is 9.82 s for community-dwelling healthy older adults [17].
BBS
BBS measurements – the 14 items on the Berg balance scale assess functional movements such as sitting, standing, and changing positions that are often performed in daily life. Every task is graded on a five-point scale ranging from 0 to 4, with 56 being the highest possible score; lower scores indicate decreased stability.
UST
It was performed by instructing the subjects to stand barefoot while lifting the other limb so that the raised foot was close to but not touching the ankle of the stance limb. Each subject was instructed to focus on a point on the wall directly in front of them, crossing their arms over their chest before elevating their limb. A stopwatch was used to record the total time the subject could stand on one leg. The time began when the subject lifted their foot off the ground, and the end time was recorded when the subject used their arms, moved their weight-bearing foot, rotated it on the ground, opened their eyes on eyes-closed trials, or a maximum of 45 s had passed. This procedure was repeated three times and recorded on the data collection sheet. The average of the three trials was calculated, and subjects with a value less than 20 s were included in the study, as specified by [18].
After screening and baseline assessment, participants were randomly assigned to one of the three groups: DT fixed- priority (group 0), DT variable-priority (group 1) and the ST training group (group 2). A familiarisation session was given to all the participants to minimise errors in assessment. All the data were kept confidential.
Intervention
All the participants received 45-min sessions for 8 weeks, 3 days per week.
Group 0 – DT training – fixed-priority (FP) included a task involving primary balance or postural control activities along with secondary cognitive activities. Instructions were given to pay attention to both balance and cognitive tasks simultaneously.
Group 1 – DT training – variable-priority (VP) participants were instructed to perform the same set of activities as those of the FP group, but under a different instructional set. One half of the training focused on postural or balance activities, and the other half focused on cognitive tasks in a single session.
Group 2 – single-task training included only balance or postural control activities.
The training interventions are listed in Table 1.
Table 1
Depicts training interventions
Statistical analysis
Data analysis was performed using IBM SPSS version 29.0 (IBM Corp.). To check the normality of the distribution, the Shapiro–Wilk test was applied to all the variables. Log transformation was applied to those variables that were not normally distributed to decrease the uniformity of error. The one-way ANOVA was employed to contrast the baseline demographic characteristics among the intervention groups. A 3×2 mixed-model analysis of variance (ANOVA) were used to statistically analyse the effect on primary and secondary outcome measures with group (ST balance training, DT training with fixed-priority instructions, DT training with variable-priority instructions) as the between-subjects factor, and time (pre-training, post-training) and testing condition (ST testing, DT testing) as within-subject factors. Partial 2 values were reported as measures of effect size. The level of statistical significance was set at p < 0.05. Where a significant group × time interaction effect was observed, post-hoc pairwise comparisons were conducted using the Bonferroni correction to control for multiple testing. The analysis was performed according to the intention-to-treat principle to preserve the benefits of the randomisation, and missing data were handled using the last observation carried forward (LOCF) method.
Results
Study selection and patient characteristics
Sixty subjects were assessed for eligibility. Out of these, 22 subjects did not meet the inclusion criteria and three refused to participate. Thirty-five subjects were selected to participate in the study and after randomisation were assigned to one of the three training groups. 12 each were allocated to the DT variable-priority group and the ST training group, whereas 11 participants were allocated to the DT fixed-priority group. Thirty-three subjects completed the training; one from the DT fixed-priority group and one from the ST training group refused to continue to participate in between the sessions. No adverse events associated with participation in the study were recorded. The CONSORT flow diagram is illustrated in Figure 1.
At the baseline assessment, no statistically significant differences were observed between the groups in terms of age, body weight, height, body mass index (BMI), waist circumference (W), hip circumference (H), or waist-to-hip ratio (W/H). The level of significance was p > 0.05 (Table 2).
Table 2
Demographic characteristics
Outcome analysis
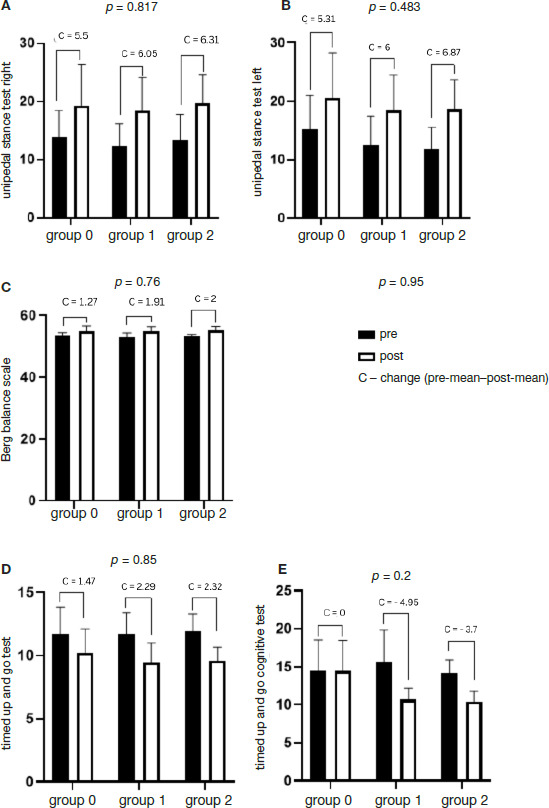
All variables except reaction time front, showed a significant main effect of time on the primary outcome measures: CoP sway EO (forward, backward, left, right) (p < 0.05), CoP sway EC (forward, backward, left, right) (p < 0.05), CoP range (forward, backward, left, right) (p < 0.05), and reaction time (backward, left, right) (p < 0.05), and the secondary outcome measures: UPST (left, right) (p < 0.01); BBS (p < 0.01), TUG (p < 0.01), and TUG-Cog (p < 0.01). There was a significant difference (p < 0.05) in the interaction (group × time) effect of some parameters of CoP sway EO and EC, reaction time, and TUG-Cog (p 0.001). However, no significant main effect of the group was observed for any of the variables (Tables 3 and 4).
Table 3
Primary outcome measure values of 3 × 2 mixed model
Table 4
Secondary outcome measure values of 3 × 2 mixed model ANOVA
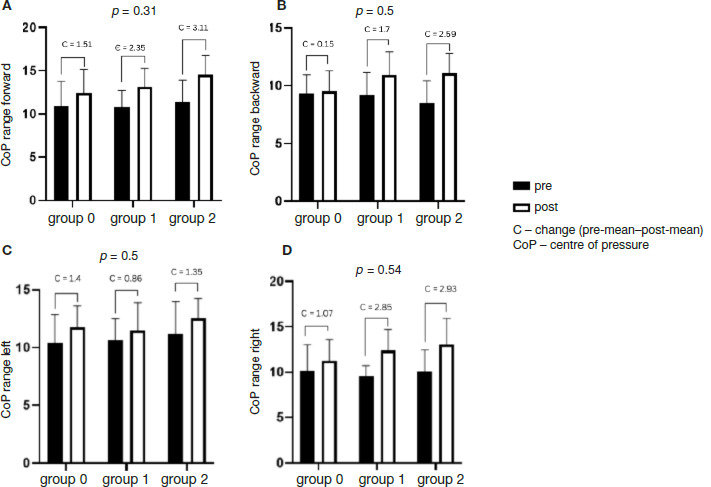
Post-hoc pairwise comparisons with Bonferroni corrections indicated that the DT variable-priority group demonstrated significantly greater improvements in the CoP sway and TUG-Cog parameters compared to the DT fixed-priority group (p < 0.05), while no significant differences were observed between the ST training group and the other groups (Figure 2–6).
Figure 2
Between-group change in means pre- and post-intervention: (A) CoP sway forward (EO) (B) CoP sway backward (EO) (C) CoP sway left Figure 2. Between-group change in means pre- and post-intervention:
(A) CoP sway forward (EO)
(B) CoP sway backward (EO)
(C) CoP sway left (EO)
(D) CoP sway right (EO)
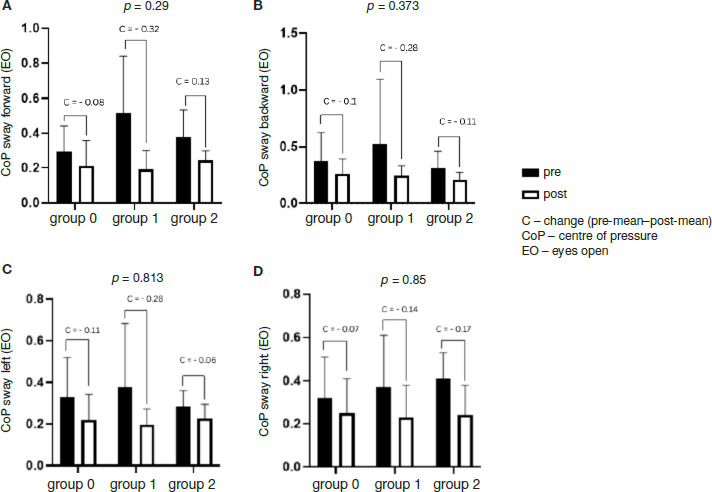
Figure 3
Between-groups change in means pre- and post-intervention:
(A) CoP sway forward (EC)
(B) CoP sway backward (EC)
(C) CoP sway left (EC)
(D) CoP sway right (EC)
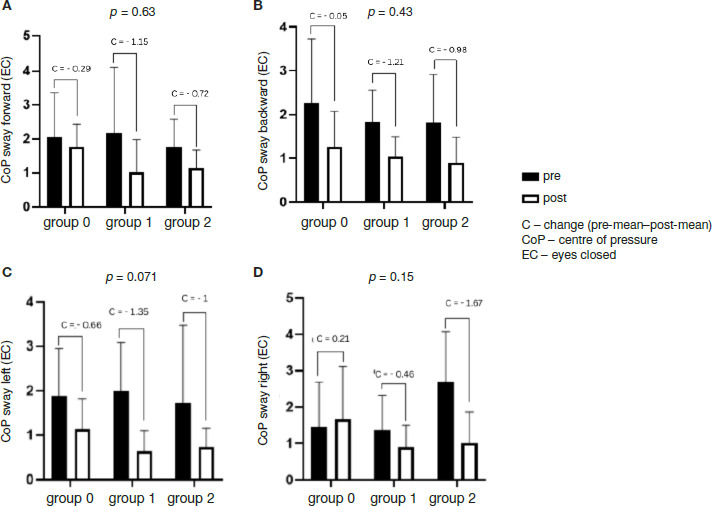
Figure 4
Between-groups change in means pre- and post-intervention:
(A) CoP range forward
(B) CoP range backward
(C) CoP range left
(D) CoP range right
Discussion
The primary aim of this investigation was to evaluate the influence of motor-cognitive dual-task (DT) training on postural stability parameters, such as CoP sway in both eyes open and closed conditions, CoP range, reaction time, and clinical tests for balance assessment, including the unipedal stance test, BBS, TUG test, and TUG-Cog test, in obese individuals. This study also aimed to identify any statistically significant differences between the DT and ST training groups and between the DT variable-priority and fixed-priority groups.
Effect of dual-task training
The present study demonstrated pronounced effects of dual-task training on balance parameters, including the UPST, BBS, TUG, and TUG-Cog tests in obese individuals after receiving 8 weeks of training intervention, which was in line with the study [19], which stated that significant improvement in balance is due to the synergistic effects of the motor and cognitive tasks in dual-task training. This synergy likely results from enhanced neuroplasticity driven by combining cognitive and physical challenges [20]. Integrating cognitive tasks with physical activities demands processing multiple information streams, which may improve attentional resource allocation and response to balance tasks [21].
As hypothesised, motor-cognitive DT training was effective in improving postural stability parameters, including CoP range, reaction time, and CoP sway in both eyes open and closed conditions. Radiological evidence using Functional Magnetic Resonance Imaging (fMRI) in the study [22] suggests that there is enhanced cerebral haemodynamics in the dorsolateral prefrontal cortex within the DT training group, while certain centres of the brain associated with DT processing showed less activation post-training, implying reduced processing demands and hence improved postural control, resulting in reduced muscle coactivation and muscle guarding, which leads to decrements in postural sway. These findings are in line with the previous studies [14, 23–31].
Dual-task vs. single-task training
The non-significant results between the DT and ST groups can be explained by the supporting task automation hypothesis. It states that concentrating on a single task at a time enables participants to automate their performance of individual tasks. This leads to a reduction in the processing demands required to perform the task, ultimately resulting in quicker development and acquisition of skills in both the ST and DT training groups [14, 30, 31]. The study [14] found no significant difference between DT variable-priority and fixed-priority groups post eight weeks of intervention, which is in line with the results of this study. These findings were also in line with the study [21], where non-significant results were noted between DT and ST training groups in patients with multiple sclerosis. The non-significant differences could also be attributed to the small sample size, lack of follow-up assessment, and the inclusion of healthy and active individuals in this study.
The alignment between these studies signifies a consistent trend across different populations and interventions. It suggests that, in certain contexts, the distinction between DT variable-priority and fixed-priority interventions may not yield significant differences in outcomes over the specified intervention period. This observation prompts further exploration into the underlying mechanisms at play and underscores the importance of considering various factors, such as population characteristics and intervention protocols, when interpreting study outcomes and designing future research endeavours. While the absence of significant differences between the DT intervention groups may appear to challenge prevailing assumptions about the benefits of attentional prioritisation strategies, it also highlights the complexity of these interactions and the need for nuanced approaches in rehabilitation and therapeutic interventions.
Dual-task variable priority vs. dual-task fixed priority
Though, non-significant results were observed in the DT variable-priority group and fixed-priority groups, greater improvement in terms of change in the mean from pre to post was seen in the DT variable-priority group among the CoP sway and TUG-Cog measures. These findings are similar to the studies [14, 31, 32], suggesting that a variable-priority instruction set in DT training shows greater improvement of balance and DT walking speed because of decreased processing demands when attention shifts between cognitive and balance activities.
However, the study [33] did not show any significant difference between the DT group with variable-priority instructions and with variable-priority progressing to fixed-priority instructions on balance, TUG-Cog, gait speed, or cognition. They cited the lack of task specificity in the protocol in order to obtain significant between-group differences as the reason.
These inconsistent findings necessitate future studies that delve deeper into elucidating the specific circumstances under which DT interventions, with varying attentional priorities, might yield differential effects on functional outcomes. Additionally, exploring potential moderators or mediators of treatment response, such as baseline cognitive function or motor impairment severity, could provide valuable insights into optimising intervention strategies tailored to individual needs and characteristics. Overall, these findings underscore the importance of continued research efforts aimed at refining and personalising rehabilitation approaches to maximise postural stability demands for obese individuals.
Limitations
There are several limitations to the study. Firstly, the small sample size restricts the generalisability of the findings and diminishes the statistical power to detect significant differences between the groups. Secondly, the predominantly female composition of our sample, consisting of relatively healthy and physically fit individuals with only mild balance impairment, hampers the extrapolation of results to male participants and those with moderate through severe balance deficits. Thirdly, the absence of a follow-up period undermines the ability to assess the longer-term effects, particularly within the two DT training groups. Future research endeavours would necessitate a larger sample size to ascertain whether clinically relevant discrepancies exist with DT training across different cohorts. Additionally, a follow-up period would be indispensable to elucidate variances between the DT variable- priority and fixed-priority groups, and to gauge the retention of training effects over time. This longitudinal perspective is crucial for understanding the sustainability of the observed improvements and informing recommendations for long-term rehabilitation and maintenance programs.
Conclusions
Following an 8-week dual-task (DT) training program that included both variable and fixed-priority instructional sets, this study demonstrates notable gains in postural stability and balance among obese individuals. Nevertheless, no benefit was observed between the variable and fixed-priority sets, and the intervention was not better than conventional single-task training. The lack of superiority over single-task training necessitates more research into the mechanisms underlying these benefits, even though these results provide insights into how well DT training improves postural stability. Furthermore, the lack of obvious advantages between fixed and variable-priority prompts the question of how best to allocate attentional resources. To find out if there are any clinically meaningful differences between these methods, more extensive studies are required.

