


Introduction
Complementary and alternative medicine (CAM) is often defined as ‘medical and health care systems, practices, and products that do not yet qualify to be part of conventional medicine’ [1]. Therapies that are included under the umbrella of ‘complementary medicine’ include biological-based therapies (food, vitamins, and other dietary supplements), manipulative and body-based techniques (such as massage, yoga, tai chi, chiropractic, and osteopathy), mind–body strategies (such as meditation, prayer, hypnosis, biofeedback, mental healing, art, music, and dance therapy), and energy interventions [2]. Alternative medicine is the term used to describe therapeutic approaches utilised instead of conventional medicine to treat or improve sickness. The term ‘alternative medicine’ encompasses a broad spectrum of medical procedures. These are typically backed by traditions not commonly taught in a medical setting in the West [3]. It is important to note that CAM encompasses both empirically supported modalities, such as massage, acupuncture, and yoga, and less verifiable practices, such as spirituality or therapeutic touch, with previous research showing varying success in evaluating these approaches and underscoring the need to distinguish between those that can be objectively tested and those that rely more on belief systems [4, 5]
In India, CAM is commonly used by doctors and patients. Compared to patients (28%), doctors (58%) were much more inclined to use complementary and alternative medicine. 52% of doctors who have personally used CAM suggested it to their patients as a treatment [6]. According to a study on oncology nurses, they generally have a favourable opinion of complementary medicine, particularly if they have had good experiences. However, they have a less favourable opinion of alternative medicine [7]. These days, physiotherapists also employ CAM techniques. The two CAM methods shown to be most effective in addressing ‘back and neck pain’, which physiotherapists most frequently treated, were massage and acupuncture [8].
Prior research has examined the attitudes, knowledge, and beliefs of medical professionals and students pursuing degrees in occupational therapy, psychology, pharmacy, nursing, chiropractic, physiotherapy, and medicine [9–12]. One study indicated that physiotherapy students believed that CAM was a good supplement to normal (Western) medicine, and that CAM provided concepts and procedures from which regular medicine could potentially improve. Fewer than one-third thought CAM posed a risk to public health. Younger physical therapists had a better opinion of CAM than older physical therapists [9]. Another study found that physiotherapy students had a low self-rated awareness of CAM [2]. This discrepancy in awareness and perspectives may indicate a generational divide and suggest a need for more integrated education about CAM in physiotherapy training.
The rising interest in CAM among healthcare professionals, particularly physiotherapists, prompts further investigation into the factors influencing their knowledge, attitudes, and beliefs. As future physiotherapists are often at the fore-front of patient care, understanding their perceptions of CAM is crucial for promoting holistic and evidence-based treatment options. This study explores the knowledge, beliefs, and influences surrounding CAM among future physiotherapists, shedding light on their readiness to incorporate these practices into their clinical settings. Through examining factors such as exposure to CAM, personal experiences, and the role of formal education, this study aims to provide valuable insights into how CAM can be integrated into physiotherapy practice in a balanced and informed manner.
Subjects and methods
Study design
An online survey with a quantitative, descriptive, cross- sectional approach was used. Google Forms was used to collect all data between March and April 2025. The approach was adapted from studies conducted at Curtin University (2019) [13] and Murdoch University (2016) [2].
Sample size
The goal was to enlist a maximum convenience sample of students. 1120 students received forms; 760 replied, yielding a 67.85% response rate. These figures are similar to those who participated in earlier surveys on the same subject [14–16].
Participants
The students were selected from various institutions in Jaipur, Rajasthan, India, that offered degrees in physiotherapy. A link to the survey was sent to the associated institutes’ faculty members. The teachers then invited the students to complete the survey during class. Students needed to be at least 17 years old, and there were no unfavourable effects of not participating. The faculty that administered the questionnaire had no involvement with the students’ instruction or assessment. Each class had a single session for data collection that lasted roughly 20 min. There were no incentives for completing the survey.
Questionnaire
The survey included the 10-item CAM Health Belief Questionnaire, which has been validated [17]. This questionnaire was used to evaluate students’ attitudes and beliefs towards CAM. Its content is also specific to medical students. The instrument’s Cronbach’s coefficient alpha was determined to be 0.75. Likert-type rating scales with seven points frame the ten questionnaire items; 1 represents ‘Absolutely Disagree’, and 7 represents ‘Absolutely Agree’. Items six, seven, and eight are reverse-scored. This instrument assessed their self-reported knowledge, CAM-related beliefs and influencing factors, and students’ propensity to suggest CAM to patients.
Statistical analysis
Means and standard deviations were used to summarise continuous variables, such as Likert scale questions, while frequency distributions were used to summarise categorical data. Independent t-tests for continuous data and chi-squared or Fisher’s exact tests, as appropriate, for categorical variables were used to analyse univariate differences between student groups. The analysis was conducted using IBM SPSS Statistics for Windows, Version 27.0 (IBM Corp., Armonk, NY, USA).
Results
The survey was completed by 760 students, of whom 350 (46.1%) were female and 410 (53.9%) were male. The participants’ mean age was 20.56 ± 1.97. Table 1 shows a comprehensive breakdown of the demographic traits of the research participants.
Table 1
Demographic characteristics of participants
| Variable | n | Frequency (%) |
|---|---|---|
| Age (mean ± SD) | 760 | 20.56 ± 1.97 |
| Sex | ||
| male | 410 | 53.9 |
| female | 350 | 46.1 |
| Academic level | ||
| UG 1st year | 144 | 18.9 |
| UG 2nd year | 240 | 31.6 |
| UG 3rd year | 202 | 26.6 |
| UG 4th year | 50 | 6.6 |
| internship | 124 | 16.3 |
According to Table 2, the modality with the highest mean knowledge score was massage therapy (2.35 ± 0.82). This indicates that students, especially those in their first and fourth years (2.84 ± 0.37 and 2.47 ± 0.85), are reasonably knowledgeable about this modality. Additionally, yoga (2.33 ± 0.84) and meditation (2.25 ± 0.80) scored highly, suggesting that the students are familiar with these practices due to their inclusion in wellness programs and their cultural significance. Lower levels of knowledge were found for hypnosis (1.52 ± 1.22), acupuncture (1.82 ± 1.09), therapeutic touch (1.79 ± 1.14), naturopathy (1.72 ± 1.10), and particularly tai chi (1.39 ± 1.23), the latter of which the students knew the least. This pattern raises the possibility that students may not fully comprehend these therapies because they are either not mentioned enough in the curriculum or are not exposed to them in clinical settings.
Table 2
Self-rated knowledge of complementary and alternative medicine
Table 3’s findings show that physiotherapy students have a generally favourable opinion of CAM’s integration into healthcare. The statement ‘Treatments not tested in a scientifically recognised manner should be discouraged’ had the highest level of agreement (mean = 5.50 ± 1.85), indicating that students favour evidence-based therapy. The acceptance that ‘complementary and alternative therapies include ideas and methods from which conventional medicine could benefit’ (5.35 ± 1.98) and support for incorporating ‘a patient’s expectations, health beliefs, and values into the patient care process’ (5.44 ± 2.01) came next, indicating a willingness to include CAM principles within the parameters of conventional care. The reasonably low score of 3.74 ± 2.09 for ‘the effects of CAM are usually due to the placebo effect’ indicates that many students recognise the possibility of genuine therapeutic effects beyond placebo. Additionally, the statement that garnered the lowest mean score (2.23 ± 1.77) was ‘CAM therapies are a threat to public health’, indicating that most students do not view CAM as detrimental but as possibly helpful when used carefully.
Table 3
Complementary and alternative medicine attitudes of physiotherapy students
Physiotherapy students’ attitudes towards CAM are significantly shaped by scientific evidence, media influence, and the opinions of physiotherapists, as seen by the bar chart in
Figure 1. According to the second pie chart (Figure 2), most respondents identify as allied health practitioners, followed by those in primary health, complementary medicine, and alternative medicine.
Figure 1
Factors that influenced the career choices of physiotherapy and counselling students, with a maximum possible score of 7 (highly influential) and a minimum score of 1 (not at all influential). Standard deviation is also shown
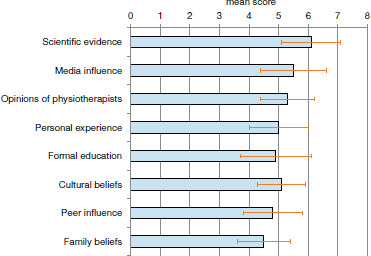
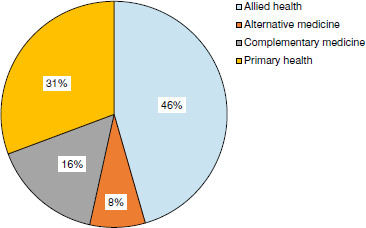
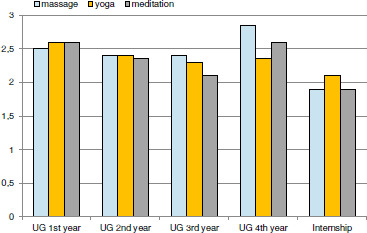
Figure 3 illustrates a visual comparison of self-assessed knowledge regarding the three most recognised CAM modalities: massage, yoga, and meditation, across academic years. The data indicate that first-year and fourth-year students exhibit greater familiarity, especially with massage and yoga, but internship-level students have a slight decrease, implying a diminished focus on these modalities throughout clinical training.
Discussion
This study aimed to assess physiotherapy students’ knowledge and attitudes towards CAM, study the variables influencing their opinions, and determine how likely they are to suggest CAM to their patients [18]. Students demonstrated strong self-rated knowledge; this aligns with the previous study, which indicated that physiotherapists may better understand CAM than physicians and nurses [19]. The findings also suggest that physiotherapy students report higher familiarity with empirically supported practices such as massage, yoga, and meditation. In contrast, modalities with limited empirical validation (e.g., spirituality) remain less well understood.
Moreover, physiotherapy education may expose students to a broader range of therapeutic techniques and philosophies that align with CAM, such as massage, yoga, and mind– body interventions. This could be explained by physiotherapy’s patient-centred, holistic approach, which frequently stresses manual, non-invasive, and supplementary treatment methods; principles that have much in common with many CAM treatments.
Physiotherapy students reported knowing more about massage, yoga, and meditation, which is similar to the findings of a previous survey, in which students reported knowing much more about massage treatment than other medical specialities [18]. Massage therapy is widely utilised as an adjunct technique in physiotherapy practice, and students often gain hands-on exposure to it during their training; however, it is not universally regarded as a core component of physiotherapy curricula across institutions. Similarly, practices like yoga and meditation, which emphasise movement, posture, breathing, and mental focus, resonate well with physiotherapy’s biopsychosocial model of health and its emphasis on patient-centred, holistic care.
The observed pattern, wherein first- and fourth-year physiotherapy students demonstrated higher familiarity and acceptance of CAM compared to their second- and third-year peers, may reflect nonlinear educational exposure and psychosocial influences rather than logical inconsistency. First-year students often enter their academic programs with pre- existing familiarity derived from community, cultural, or media exposure to widely practised modalities such as yoga and meditation, which hold deep roots in Indian wellness traditions. During the second and third years, the academic focus typically shifts towards foundational biomedical subjects – such as anatomy, physiology, and pathology – where the emphasis on conventional scientific paradigms may temporarily diminish the interest in or perceived credibility of non- mainstream practices. In contrast, fourth-year students, nearing the culmination of their coursework, are reintroduced to broader therapeutic frameworks through clinical electives and rehabilitation modules that highlight integrative and patient-centred approaches, which may renew their appreciation for CAM’s complementary potential. Internship students, however, often engage in intensive, evidence-driven clinical rotations that prioritise conventional physiotherapy practices, leading to relatively reduced engagement with CAM. This oscillating trend of awareness and acceptance aligns with previous research among medical and allied health students, which has reported similar ‘fluctuating attitudes’ towards CAM across different academic phases as a function of exposure, scepticism, and clinical experience [2, 14]. The integration of patients’ beliefs, values, and expectations into the care process was generally well-received by physiotherapy students, with the highest level of agreement (mean = 5.44 ± 2.01). This finding aligns with the findings of Armson [2], who found that physiotherapy students overwhelmingly agreed that considering patients’ viewpoints is essential to providing health-care. Interestingly, while there was support for discouraging scientifically unverified treatments (mean = 5.50 ± 1.85), students simultaneously held positive views about CAM’s natural healing capacity (mean = 4.88 ± 2.14). This apparent contradiction mirrors earlier studies, which noted that students might support evidence-based scepticism while maintaining a generally favourable opinion towards CAM’s potential [13].
This also reflects a pronounced inclination towards evidence-based decision-making among future physiotherapists. Such an attitude signals a potential shift in clinical practice, where students may increasingly question or refrain from using modalities with limited or inconclusive scientific support. This discerning stance may extend to treatments traditionally used in physiotherapy but whose efficacy remains debatable, such as transcutaneous electrical nerve stimulation (TENS) [20], therapeutic ultrasound [21], and kinesio-taping [22]. Suppose this cautious, evidence-focused perspective carries forward into professional practice. In that case, it may contribute to a gradual departure from legacy interventions that lack robust empirical backing, marking an evolution in physiotherapy driven by critical appraisal and research literacy.
Unlike previous studies where personal experience and scientific evidence were identified as the most influential factors shaping attitudes towards CAM among nursing, chiropractic, physiotherapy, and counselling students [2, 13], the findings of our study show a slightly different trend. In the current study, scientific evidence remained a highly influential factor in shaping physiotherapy students’ beliefs about CAM. However, media influence and the opinions of physiotherapists also emerged as strong determinants of student attitudes, indicating a broader set of influences in the contemporary educational and clinical environment. This variation may reflect differences in curricular exposure, clinical mentorship, or the evolving role of digital media and professional networks in shaping health professional knowledge.
The results of this study offer important new information about how physiotherapy students view their careers in connection with various healthcare paradigms. Most students identified as allied health professionals, which supports how physiotherapy is currently framed in school and clinical settings as a fundamental aspect of the allied health industry. This aligns with worldwide norms that acknowledge physiotherapists as movement specialists who support patients’ functional rehabilitation and multidisciplinary care teams. A significant number of students thought of themselves as employed in primary health care. This is in line with expanding worldwide trends that support the inclusion of physiotherapists in primary care systems, particularly for treating chronic and musculoskeletal disorders. Fewer students aligned themselves with CAM, possibly indicating that while physiotherapy might utilise techniques of CAM (e.g., dry needling, yoga, cupping), students still view their profession as more science-based and integrative with mainstream health-care than the alternative. The problem of patient disclosure about the use of CAM is a significant element that surfaced from the more extensive literature but was not explicitly evaluated in this study. Previous research has indicated a considerable communication gap; according to reports, only 72% of patients tell their doctor they utilise CAM [23]. This lack of openness may have profound clinical repercussions, especially when CAM combines with traditional treatments and results in unfavourable outcomes [24]. However, according to some research, 71% of physiotherapists say they know that their patients utilise CAM services, and most ask about it during evaluations [8]. This discrepancy between practitioner assumptions and patient non-disclosure highlights a communication gap that aspiring physiotherapists need to be ready to handle. Although this current study did not directly measure disclosure practices, the findings related to the knowledge, beliefs, and influences of CAM among future physiotherapists highlight the importance of a professional culture that values open dialogue, critical appraisal of evidence of CAM, and patient-centred care. It should also be noted that the relatively large standard deviations observed in Tables 2 and 3 indicate considerable variability in students’ responses. This heterogeneity likely reflects differences in individual exposure to CAM across institutions and years of study, and it limits the extent to which the findings can be generalised to the wider physiotherapy student community.
Limitations
This study has several limitations, including its reliance on self-reported data, which may introduce bias, and its cross- sectional design, which limits causal interpretations. The use of convenience sampling restricts generalisability beyond the selected institutions. Additionally, the study did not explore CAM disclosure practices or validate the questionnaire specifically for physiotherapy students.
Conclusions
This study offers insight into future physiotherapists’ CAM- related knowledge, attitudes, and influencing factors. According to the results, physiotherapy students have a favourable opinion of CAM, especially those practices that complement their holistic education, such as massage, yoga, and meditation. Physiotherapy students appear more confident in empirically supported CAM practices, while approaches lacking robust evidence should be integrated cautiously. Future educational programs should emphasise this distinction to ensure that evidence-based practices are prioritised within physiotherapy training.

