

Introduction
Post-traumatic stress disorder (PTSD) is a complex neurologic condition with far-reaching effects on mental health. It poses a significant clinical challenge, due to its high prevalence – conservatively estimated at 8% [1] – and its resistance to successful treatment. Our pathophysiologic understanding of PTSD remains limited, and the role of autonomic nervous system dysregulation in this condition has only recently begun to be elucidated. Latest large-scale humanitarian crises, such as the war in Ukraine, have further underscored the growing clinical burden of trauma-related disorders and the corresponding need for mental health interventions [2].
According to the DSM-5 classification [3], PTSD symptoms are grouped into four main categories: intrusive memories, avoidance, hyperarousal, and negative changes in mood and thinking. Intrusions involve recurrent and distressing memories of the traumatic event, including flashbacks and trauma-related nightmares. Avoidance refers to deliberate efforts to evade thoughts, emotions, people, places, or situations associated with the traumatic experience. In turn, hyperarousal is characterised by persistent physiological activation, manifested as irritability, hypervigilance, sleep disturbances, and exaggerated emotional reactions, such as anger outbursts. Finally, negative alterations in mood and cognition include persistent feelings of guilt, social withdrawal, emotional numbing, and enduring negative beliefs about oneself or the world [3–5]. At the same time, specific categories of traumatic events have been identified which can precipitate the onset of PTSD [5]. The disorder develops following exposure to actual or threatened death, serious injury, or sexual violence, and this exposure may occur directly or through witnessing traumatic events. Common examples include interpersonal violence, serious accidents, war-related experiences, terrorist attacks, and sudden loss of a loved one. However, the specific pattern or severity of symptoms depend less on the type of traumatic event itself than on individual vulnerability, neurobiological factors, and contextual influences.
The pathophysiology of PTSD is defined by frontolimbic dysregulation, characterised by amygdala hyperactivity and impaired top-down control from the prefrontal cortex [6–8]. These structural and functional aberrations, often exacerbated by HPA-axis dysregulation and hippocampal atrophy, form a neurobiological substrate for treatment resistance [9–13]. This necessitates a shift towards therapeutic strategies that directly modulate these neural networks, moving beyond traditional pharmacotherapy and psychotherapy [14–16].
Neuroimaging studies have further identified changes in other brain structures, such as the cingulate cortex, insula, and brainstem structures, which modulate autonomic responses, anxiety, and emotional memory. Abnormalities in the limbic system and frontolimbic pathways suggest impaired communication between brain regions governing emotional processing and rational assessment of situations [17].
The pathophysiology of PTSD therefore involves complex disturbances in the functioning of neural networks involved in emotion processing, memory, and stress response regulation. Understanding these mechanisms is crucial for the development of modern therapeutic methods.
Treatment of PTSD primarily involves pharmacotherapy and/or psychotherapy, with the choice of treatment approach tailored to the type and severity of symptoms and the individual needs of the patient.
In addition to PTSD, the International Classification of Diseases (ICD-11 [18]) also distinguishes a complex post-traumatic stress disorder (CPTSD), which is, however, not classified in DSM-5. CPTSD most often develops as a result of prolonged or repeated life-threatening events of a terrifying nature where escape is impossible or difficult, such as torture, slavery, acts of genocide, domestic violence, and repeated sexual abuse in childhood [19]. In individuals with CPTSD, these events trigger the same symptoms as those observed in PTSD, i.e., flashbacks, hypervigilance, and avoidance of trauma-related reminders. Additional difficulties in interpersonal relationships, emotional dysregulation, and an unstable self-image and identity can also be observed in this population of patients [20].
Pharmacotherapy is a supportive method used to alleviate anxiety, depressive symptoms, and sleep disorders associated with PTSD. The first-line drugs are selective serotonin reuptake inhibitors (SSRIs), such as sertraline or paroxetine, which have been shown to be effective in numerous clinical studies [21]. In turn, serotonin–norepinephrine reuptake inhibitors (SNRIs), such as venlafaxine, are recommended when SSRIs are ineffective or depressive symptoms coexist [22]. Prazosin may also be helpful in treating sleep disorders and nightmares [23].
Currently, the most effective psychotherapeutic methods include prolonged exposure (PE) therapy, trauma-focused cognitive-behavioural therapy (TF-CBT), and Eye Movement Desensitization and Reprocessing (EMDR) [24]. Exposure therapy involves gradually confronting the patient in a controlled environment with stimuli reminiscent of traumatic events, which leads to a reduction in intrusive memories and avoidance behaviours [25]. TF-CBT integrates elements of cognitive and behavioural therapy, allowing for the modification of harmful thought and emotional patterns, and has demonstrated high efficacy in treating children, adolescents, and adults with PTSD [26]. EMDR is a therapeutic method that combines elements of exposure and cognitive therapy with bilateral stimulation (e.g., eye movements, tapping, or auditory cues), while focusing on the traumatic event, enabling the patient to process traumatic memories and reduce PTSD symptoms [27].
PTSD treatment can be effective, with remission rates reported to be as high as 40–60% [28], although other studies have reported lower success rates [29]. The effectiveness of PTSD treatment likely depends on an individual’s response to the therapeutic method employed and their symptom profile. Moreover, combining psychotherapy, pharmacotherapy, and modern technological solutions can increase treatment effectiveness, improving the quality of life of individuals suffering from PTSD, as confirmed in a review of published studies [30].
In recent years, the importance of modern technologies supporting PTSD therapy has been growing. Virtual Reality Exposure Therapy (VRET) allows for the safe recreation of traumatic situations within a controlled virtual environment, enabling effective processing of anxiety-inducing stimuli [31]. Additionally, neurorehabilitation and neuromodulation techniques are increasingly used to normalize brain activity and improve the cognitive and emotional functioning of patients. Neuromodulation involves modifying electrical activity of neurons in the central or peripheral nervous system. The term “neurorehabilitation” refers to a set of clinical interventions that deliberately affect brain function by harnessing neuro-plasticity mechanisms triggered by neural activity and experience. According to Edelman’s Law, neuroplasticity occurs primarily through synaptic changes, which in turn lead to permanent structural changes in the brain [32]. Age is an important factor modulating this process. Studies have shown that even in adults, significant chemical and structural changes are likely in selected regions of the central nervous system, which determines the effectiveness of targeted rehabilitation interventions in this group [33].
Contemporary neurorehabilitation also draws on innovative technologies that enable precise monitoring and stimulation of neuronal activity. One example is brain-computer interface (BCI) technology, which enables real-time tracking of brain activity and tailoring therapy parameters to the individual patient needs. In turn, the use of virtual reality (VR) environments in rehabilitation opens new possibilities for stimulating the nervous system, creating immersive conditions that enhance neuroplasticity. Magnetic resonance imaging (voxel- based morphometry) studies have shown that the VR therapy can lead to an increase in grey matter volume in structures such as the hippocampus, caudate nucleus, parietal cortex, and visual cortex, providing neuroanatomical evidence for the effectiveness of this type of intervention [34]. Integrated VR systems combining elements of motor training with cognitive tasks have a significant impact on improving both motor functions and cognitive abilities in neurological patients [35, 36]. Newer VR systems that focus on increasing patient motivation and engagement have also been proven effective in improving cognitive function, mood, and the overall quality of rehabilitation [37].
Such technologies enable a more precise, personalised approach to rehabilitation, and their effectiveness is based on reinforcing neuroplasticity mechanisms, which is confirmed by both neuroimaging findings and clinical studies. These approaches represent novel tools in the diagnosis and treatment of the post-traumatic stress disorder.
While systematic reviews are available for individual techniques such as tDCS, rTMS, or VR, there is a lack of synthesis that integrates these findings across adult populations with clinically diagnosed PTSD, including CPTSD. This work aims to address this gap by offering a holistic view of the neuro-modulation landscape. Such a synthesis is crucial for clinicians facing the challenge of choosing the appropriate technique based on comparable evidence quality, rather than relying on isolated results for a single method.
The aim of this study was, therefore, to synthesise and evaluate existing evidence from systematic reviews and meta-analyses regarding neurorehabilitation- and neuromodulation-based interventions in adults with PTSD.
Subjects and methods
This umbrella review follows the Joanna Briggs Institute (JBI) methodology to provide a transparent and structured synthesis of evidence within the field of neuropsychiatry [38, 39]. A comprehensive literature search was conducted between January and March 2026 in PubMed, Web of Science, and Google Scholar, covering peer-reviewed publications from 2000 to 2025 (last access on March 13, 2026). The year 2000 was selected as the starting point because it coincides with the emergence of modern neuromodulation techniques such as transcranial direct current stimulation (tDCS), repetitive transcranial magnetic stimulation (rTMS), EEG-neuro-feedback (EEG-NF), real-time fMRI neurofeedback (fMRI-NF), and the first clinical applications of VR and BCI technologies relevant to PTSD research. For the purpose of this review, the term “neuromodulation” is used in an operational sense, referring to non-invasive techniques (tDCS, rTMS) and virtual reality (VR) technologies that directly or indirectly influence central nervous system activity to modulate emotional and cognitive responses, excluding standard pharmacological and physical therapy methods. Standard Boolean operators and/ or were used to combine search terms related to trauma psychopathology and neuromodulation, including PTSD, CPTSD, neuromodulation, virtual reality, EEG-NF, fMRI-NF, tDCS, rTMS, VR-based therapy, BCI, and eye-tracking. Finally, two terms were used: PTSD and neurorehabilitation. The study selection process is presented in the flow diagram in Figure 1.
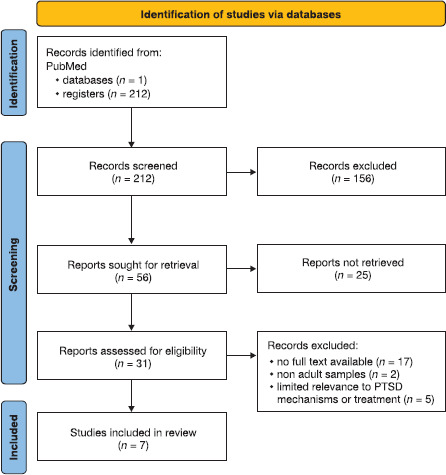
The search initially identified 212 records. Full-text assessment was based on predefined criteria: adult samples with DSM-5 or ICD-11 PTSD/CPTSD; use of neuromodulatory or technology-assisted interventions; availability of quantitative clinical, neurophysiological or neuroanatomical outcomes; and publication in English-language peer-reviewed journals. Exclusion criteria included: full-texts not available, animal studies, articles outside the scope of the review, studies lacking measurable outcomes, and case reports.
A total of 7 studies met inclusion criteria. These consisted of 4 VR-based interventions (classified as indirect neuro-modulation – a cognitive approach based on mechanisms such as pain gating, distraction, and neuroplasticity), 1 tDCS intervention, and 2 rTMS interventions (classified as direct neuromodulations). The high number of excluded studies (n = 205) was primarily due to a lack of quantitative outcomes, non-adult samples, descriptive design, or limited relevance to PTSD mechanisms or treatment. Additional references cited throughout the article were included solely to provide background information on neurobiology, epidemiology, diagnostic systems, and pathophysiology of PTSD and were not considered part of the included evidence base synthesised in this umbrella review.
Given the substantial methodological and technological heterogeneity, we adopted a narrative synthesis approach to integrate findings within a neurobiological framework emphasising frontolimbic dysregulation, impaired neuroplasti-city, and attentional disturbances characteristic of PTSD.
To assess the methodological quality of the included systematic reviews and meta-analyses, we utilised the JBI Critical Appraisal Checklist. This tool is widely recognised as a standard for assessing research rigor, enabling the identification of potential methodological biases that could have influenced the findings. The assessment process involved verification against the 11 items included in the JBI checklist, which allowed for a thorough evaluation of each included study. The results of this assessment are summarised in Table 1, and the conclusions were used to differentiate the quality of evidence during data synthesis in the Discussion section.
Table 1
Characteristics of the included studies
| Authors (year) | JBI assessment | Intervention | Design | Number of studies | Main findings |
|---|---|---|---|---|---|
| Miltiadis et al. (2025) [38] | moderate | VR | review | 19 | VR has the potential to emerge as a pivotal tool in personalized medicine, offering innovative solutions for complex neurological and mental health challenges – depression and PTSD. |
| Wankhede et al. (2025) [39] | moderate | VR | review | 6 | VR has the potential as an innovative and effective tool in neurological rehabilitation in PTSD and depression. |
| Shen et al. (2025) [40] | high | VR + CBT | review | 13 | VR interventions may improve specific cognitive domains including attention, memory, and executive function in PTSD or TBI, especially when integrated with Cognitive Behavioural Therapy. |
| Lindsey et al. (2022) [41] | moderate | rTMS | review | 8 | rTMS neurostimulation has the potential to alter neural networks in a manner that may benefit special populations with PTSD or TBI. |
| Thibaut et al. (2021) [42] | high | tDCS | review | 3 | tDCS represents a valuable treatment for chronic neuropathic pain, psychiatric disorders, PTSD, and depression |
| Oberman et al. (2020) [43] | high | rTMS | review | 4 | rTMS exerts positive effects in the treatment of neuropsychiatric PTSD; however, evidence for neurocognitive symptoms is limited |
| Cieślik et al. (2020) [44] | high | VR | review | 70 | VR therapy exerts positive effects in the treatment of anxiety disorders and PTSD |
Results
The results of the synthesis are summarised in Table 1 which presents the characteristics of the included studies, including intervention type, study design, and key findings. Additionally, the PICO-based characteristics of these inter- Figure 1. Study selection (in accordance with the PRISMA 2020 guidelines) ventions are presented in detail in Table S1 in the Supplementary materials section.
Virtual reality
Virtual reality is an innovative technique used in neurorehabilitation that enables the creation of immersive, task-specific environments tailored to therapeutic goals. Evidence suggests that VR may promote neuroplasticity by facilitating changes in synaptic connections and activating cortical and subcortical networks involved in motor, sensory, and cognitive processing. As a result, VR interventions may improve cognitive functioning such as memory, attention, learning, and emotional regulation [45, 46].
The results of the present review indicate that VR is increasingly applied in neurorehabilitation, particularly in patients with PTSD and related disorders. Several systematic reviews included in the analysis provide consistent, although heterogeneous, evidence of its effectiveness.
The largest review, conducted by Cieślik et al. [44], included 70 studies and demonstrated that VR-based interventions exert beneficial effects in the treatment of PTSD and anxiety disorders. These effects were primarily related to symptom reduction, especially in terms of anxiety and emotional dysregulation.
More recent reviews confirm these findings. Shen et al. [40], analysing 13 studies, showed that VR, particularly when combined with cognitive behavioural therapy, can not only alleviate PTSD symptoms but also improve specific cognitive domains such as attention, memory, and executive functions. These findings suggest that VR may enhance the effects of psychotherapy by increasing patient engagement and facilitating exposure-based mechanisms.
Similarly, Miltiadis et al. [38], in a review of 19 studies, highlighted the broad applicability of VR across psychiatric conditions, including PTSD and depression. They emphasised the potential of VR as a tool for personalised medicine, allowing for individualised therapeutic scenarios and adaptive treatment protocols.
Wankhede et al. [39], based on 6 studies, also reported that VR is a promising and innovative approach in neurorehabilitation, particularly in reducing PTSD symptoms. However, they noted that the relatively small number of studies and variability in methodologies limit the strength of these conclusions.
Overall, although the reviewed studies consistently indicate positive effects of VR in mitigating PTSD symptoms and improving cognitive functioning, there is substantial heterogeneity in study designs, intervention protocols (e.g., type of VR environment, duration, and integration with psychotherapy), and outcome measures. This variability underscores the need for further large-scale, standardised trials to better define the efficacy and optimal application of VR in PTSD treatment [47].
Transcranial direct current stimulation
Transcranial direct current stimulation is a neuromodulation technique that involves delivering low-intensity current to cortical regions of the brain, thereby either activating or inhibiting neuronal activity. The underlying mechanism involves shifting neuronal membrane potential towards depolarisation or hyperpolarisation [48]. Anodal stimulation causes depolarisation and increases the likelihood of generating action potentials, whereas cathodal stimulation leads to the hyperpolarisation of neuronal cell membranes. A standard tDCS therapy session usually lasts about 10–20 min.
For several years, detailed studies have been conducted on the effectiveness of tDCS in psychiatric and neurological disorders. In a randomized study, patients diagnosed with depression underwent sequential sessions of high-definition (HD) tDCS targeting the left dorsolateral prefrontal cortex (LDLPFC) [49]. Structural MR analysis was employed to assess the impact of treatment, and significant increases in grey matter volume occurred not only at the stimulation sites but also in related areas such as the bilateral DLPFC, posterior cingulate cortex, posterior parietal cortex, right caudate nucleus, hippocampus, and thalamus [48]. Other studies [50, 51] indicate smaller structural effects involving only a slight expansion of grey matter in the studied brain regions.
tDCS may have a positive effect in reducing PTSD symptoms. In a randomised, double-blind clinical trial [52], 40 participants with PTSD were randomly assigned to a group receiving 10 sessions of tDCS (2 mA, DLPFC) or a placebo group. tDCS therapy significantly reduced symptoms of hyperarousal, anxiety, negative cognitive variables, and mood compared to those in the placebo group, but the differences in avoidance symptoms were not significant. A recent study on war veterans, combining tDCS with VR-mediated exposure therapy, revealed a reduction in PTSD symptoms and autonomic nervous system arousal [53]. The therapeutic rationale of tDCS in PTSD is based on the modulation of cortical excitability, particularly within prefrontal regions involved in emotional regulation and cognitive control. Typical protocols involve repeated sessions with low-intensity current (1–2 mA), although optimal dosing parameters remain unclear. The method is safe, portable, and relatively inexpensive, which supports its feasibility in outpatient settings; however, variability in protocols and inconsistent clinical outcomes present challenges for routine implementation.
In the present review, only one review study met the inclusion criteria. This included review primarily focused on burn- related symptoms, with an emphasis on physical pain, although it also addressed mental health conditions such as PTSD. It synthesised only 3 studies out of 21 identified publications, highlighting the paucity of research in this specific area. These findings suggest that tDCS is a relatively novel therapeutic approach in the context of post-burn rehabilitation. Although the results indicate potential effectiveness in reducing PTSD symptoms, the outcomes across the available studies remain inconsistent.
Repetitive transcranial magnetic stimulation
Repetitive Transcranial Magnetic Stimulation is a neuro-modulation technique that modulates neuronal excitability by delivering magnetic pulses to specific areas of the cerebral cortex. In the context of PTSD, the most stimulated area is the right dorsolateral prefrontal cortex (RDLPFC), which aims to modulate frontolimbic connections and reduce the excessive reactivity of limbic structures such as the amygdala. In one of the first randomized placebo-controlled studies, Cohen et al. [54] showed that 10 Hz stimulation of the R-DLPFC led to a significant reduction in PTSD and anxiety symptoms compared to low-frequency and sham rTMS. In turn, Watts et al. [55] used a 1 Hz protocol in the same location, also achieving a significant reduction in symptoms, although part of the effect disappeared after a few weeks.
More recent studies have confirmed that combining rTMS with psychotherapy can increase the effectiveness of treatment. In 2018, Lantrip [56] conducted a randomized study involving veterans in which rTMS (1 Hz, R-DLPFC) administered prior to cognitive trauma therapy (CPT) sessions led to significantly greater improvement than CPT combined with placebo, with the effect lasting up to 6 months. Isserles et al. [57] applied deep transcranial magnetic stimulation (dTMS) directed at the prefrontal region in combination with brief exposure to traumatic stimuli. This multicentre study demonstrated the efficacy and safety of this protocol, confirming the validity of integrating neuromodulation with exposure therapy.
rTMS presents a viable option for integration into PTSD treatment in clinical practice. It may be especially effective in combination with psychotherapy. Successful implementation in everyday practice requires equipment, trained clinicians, and PTSD-specific stimulation protocols. Continued research is necessary to develop these protocols, identify patients who would benefit from rTMS, and assess long-term effectiveness.
This review included only two publications that met the inclusion criteria. Lindsey et al. [41] focused on the use of rTMS and iTBS in cognitive rehabilitation for depression and PTSD. The results across studies were not always consistent. While rTMS appeared to be effective in reducing PTSD symptoms in some studies, other trials reported no significant effects. Importantly, the review emphasised the safety profile of rTMS, noting exclusion criteria such as the presence of metal implants in the face, head, or eyes. In clinical trials involving U.S. veterans, rTMS was similarly found not to produce consistent benefits: although one study reported statistically significant reductions in PTSD symptoms, the overall conclusion was that rTMS effectiveness remains variable and requires further standardization to ensure reliable clinical outcomes.
Discussion
Among the modern neuromodulation methods employed in the treatment of the post-traumatic stress disorder (PTSD), three approaches are gaining increasing importance: VR, tDCS, and rTMS. Although they all aim to improve emotional regulation and reduce clinical symptoms in PTSD, they differ in their mechanisms of action, level of empirical support, and feasibility of implementation in clinical practice.
A critical synthesis of the available literature suggests that all three methods demonstrate potential efficacy, particularly in reducing core PTSD symptoms such as hyperarousal, anxiety, and impaired emotional regulation. However, their clinical utility remains limited by methodological heterogeneity, small sample sizes, and insufficient long-term follow-up data. Recent meta-analyses indicate that while neuromodulation techniques (including rTMS and tDCS) can produce short-term symptom reduction, evidence for sustained therapeutic effects remains inconsistent [58, 59].
Current evidence suggests that VR represents a promising adjunctive modality in neurorehabilitation. Research indicates that VR-based interventions may facilitate neural plasticity, potentially contributing to a reduction in PTSD symptom severity [39, 43]. This is corroborated by recent findings, which demonstrate that VR applications can alleviate anxiety and enhance cognitive function in TBI populations [60–62]. Furthermore, literature underscores that VR enables highly personalised, patient-centred therapy, generally associated with high levels of patient acceptance and engagement [38]. Nevertheless, given the significant methodological heterogeneity observed across existing studies, these findings should be interpreted with caution [39]. Consequently, VR may be best conceptualised as a therapeutic adjunct that fosters emotional engagement and facilitates controlled, safe exposure therapy. Further high-quality research is required to delineate the patient-specific factors that optimize therapeutic outcomes.
Transcranial direct current stimulation, in turn, offers a relatively simple, low-cost, and portable method of modulating cortical excitability, especially within prefrontal regions implicated in top-down emotional regulation. Although several studies reported reductions in anxiety and depressive symptoms, the overall evidence in PTSD populations remains inconclusive, with high variability in stimulation parameters (e.g., intensity, electrode placement, session number). Meta-analytic data suggest that tDCS effects may be modest and highly dependent on protocol design and patient characteristics [63]. Additionally, replicability remains a major concern, thus limiting its current applicability as a standard clinical intervention.
Among the reviewed methods, rTMS is the most extensively studied and clinically established, particularly due to its approval in the treatment of major depressive disorder. Evidence indicates that stimulation of the right dorsolateral pre-frontal cortex (DLPFC) can modulate frontolimbic circuits and reduce PTSD symptoms. Nevertheless, meta-analyses report mixed results, with some studies showing moderate benefits and others indicating minimal differences compared to sham stimulation [63]. Importantly, the strongest effects are observed when rTMS is combined with psychotherapy, suggesting a synergistic mechanism involving enhanced neuroplasticity and improved engagement in trauma processing [65].
From a neurobiological perspective, the observed effects of neuromodulation techniques may be explained by their impact on frontolimbic dysregulation, being a core feature of PTSD. By modulating activity in the prefrontal cortex, amygdala, and hippocampus, these interventions may facilitate fear extinction, improve emotional regulation, and partially reverse trauma-related neuroplastic changes. However, direct evidence linking clinical improvement with neurobiological normalization remains limited, thus more multimodal studies (e.g., combining neuroimaging with clinical outcomes) are needed.
An important limitation of the current evidence base is the short duration of follow-up in most studies, which makes it difficult to assess the durability of treatment effects. Many interventions show initial improvement, but symptom relapse after several weeks or months is common, suggesting that maintenance protocols or booster sessions may be necessary. Additionally, patient heterogeneity (e.g., trauma type, comorbidities, chronicity of PTSD) is rarely controlled for, further complicating the interpretation of results.
Another key issue is the lack of standardised outcome measures across studies. While some studies focus on symptom severity scales (e.g., CAPS, PCL-5), others assess cognitive or neurophysiological outcomes, limiting comparability and synthesis of findings [66]. Future research should aim to establish uniform clinical endpoints and reporting standards.
From a clinical perspective, neuromodulation techniques should currently be considered adjunctive rather than first-line treatments. Hence, their integration with evidence-based psychotherapies, such as trauma-focused cognitive-behavioural therapy or EMDR, appears to be the most promising approach. In particular, combining neuromodulation with virtual reality (VR), brain-computer interfaces (BCI), and real-time feedback systems may enhance personalisation of therapy and improve patient engagement.
In recent years, the importance of eye-tracking methods has also been growing, as they allow for an objective assessment of visual attention patterns in patients with PTSD. Studies have shown that individuals with PTSD are characterised by prolonged fixation on negative stimuli [67], maintaining attention on threatening scenes [68], and shortened scanning trajectories in tasks with a high cognitive load [69]. The most consistent phenomenon in PTSD is sustained attention to threatening stimuli, which distinguishes individuals with the disorder from the general population [70]. These results suggest the possibility of using eye-tracking integration with VR systems to personalise therapy, monitor attention in real time, and implement adaptive training strategies aimed at modifying dysfunctional patterns of emotional stimulus processing. The use of these advanced technologies in PTSD therapy, due to their potential to buttress the neurorehabilitation processes, could improve treatment effectiveness [32, 33, 35].
From a clinical perspective, it is also worth considering the cost-benefit ratio of using these interventions. The literature lacks standardised economic data for the neuromodulation methods included. Consequently, it is essential to consider clinical feasibility, which in practice determines the accessibility of these methods for patients. In the case of rTMS, one must consider a high barrier to entry (specialisd equipment, a dedicated facility, and constant supervision by qualified medical personnel). However, despite high direct costs, this method is characterised by high focal precision and documented efficacy in chronic conditions, which justifies its use in specialised centres. In contrast, for tDCS, financial and logistical barriers are significantly lower. The devices are relatively inexpensive, portable, and, in certain protocols, allow for supervised home-based therapy, which significantly lowers operational costs and increases treatment accessibility. VR occupies an intermediate position; although it requires investment in hardware and software, it offers the unique benefit of deep patient engagement and high interactivity, which may reduce the duration of rehabilitation required to achieve therapeutic outcomes. It is evident, however, that from a clinical perspective, the choice between these methods should not be dictated solely by device costs, but primarily by the patient’s profile, the availability of human resources, and the expected therapeutic goal. Cost optimisation in neuromodulation appears to lie in the precise matching of the method to the patient’s needs, thus avoiding the unjustified use of expensive procedures in cases where less costly methods (e.g., tDCS or VR) could be equally effective.
Despite promising results, neuromodulation for PTSD remains an adjunctive therapy rather than a replacement for psychotherapy. Future research avenues should include large-scale, long-term follow-up multicentre randomised controlled trials, based on the standardisation of stimulation protocols. It would also be important to identify the predictors of treatment response (e.g., biomarkers, neuroimaging profiles) and the investigations of combined and multimodal interventions.
Limitations
Despite a comprehensive analysis of the collected data spanning 25 years, certain limitations should be taken into account. These include methodological heterogeneity in studies on neuromodulation in PTSD (e.g., methods used, study population, study protocols). This makes it difficult to directly compare results and draw unambiguous conclusions. Furthermore, this umbrella review indicates that while most interventions showed short-term improvement, follow-up studies were lacking. Additionally, in some studies, there is a noticeable risk of publication bias, characterised by the overrepresentation of positive results. Moreover, despite the overview of numerous studies (212 studies described regarding VR, tDCS, and rTMS), the final analysis was conducted on 7 review studies, which necessitates cautious interpretation. It can, therefore, be concluded that, at present, no definitive conclusions can be drawn regarding the clinical efficacy of the presented methods, hence they should be treated as adjunctive therapies rather than first-line treatments.
Conclusions
In summary, all the three discussed methods of neuro-modulation show therapeutic potential in the treatment of PTSD. However, differences in the degree of empirical confirmation and barriers to practical implementation must be considered. VR and tDCS remain experimental techniques with a growing number of studies, while rTMS is the most established tool, though still requiring further standardisation of protocols in the context of PTSD. It is, therefore, necessary to seek and develop innovative therapeutic approaches that can effectively support the recovery process of PTSD patients. The integration of various forms of neuromodulation with psychotherapy and cognitive rehabilitation may be a promising direction, allowing for better tailoring of interventions to the individual needs of individuals suffering from PTSD. Overall, although individual neuromodulation approaches differ in their mechanisms, feasibility, and resource requirements, their clinical application in neurorehabilitation requires careful consideration of accessibility, cost, and implementation constraints. Importantly, beyond symptom reduction, their potential to improve functional outcomes remains a key aspect from a physiotherapy perspective.

